

Our Mission
PeopleBeatingCancer supports an evidence-based integrative approach to cancer care. For most newly diagnosed patients, FDA-approved therapies form the foundation of treatment, while evidence-based complementary therapies may help reduce side effects and improve survivorship.
Click the orange button to the right to learn more.
- You are here:
- Home »
- Blog »
- Multiple Myeloma »
- Bone Health in Multiple Myeloma: What Patients Need to Know
Bone Health in Multiple Myeloma: What Patients Need to Know
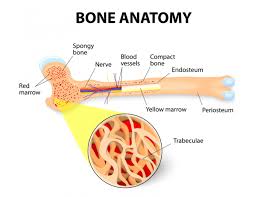

Bone Health in Multiple Myeloma: What Patients Need to Know. Multiple myeloma can be as much a disease of the bones as it is a disease of the blood. Bone lesions, osteoporosis, fractures, spinal compression fractures and bone pain can affect quality of life long after a patient’s initial diagnosis and treatment.
The good news is that myeloma-related bone disease is not something patients have to accept.
- Modern myeloma treatment includes medications designed to reduce skeletal complications.
- Imaging has become much more sensitive.
- Radiation and orthopedic procedures can help manage serious bone problems.
- Exercise, nutrition, vitamin D, physical therapy, and other supportive strategies may help patients preserve strength, mobility, and quality of life.
This guide brings together PeopleBeatingCancer’s most useful articles about multiple myeloma bone health, bone pain, bone lesions, fractures, bone-strengthening therapies and long-term skeletal health.
Important: Bone health management in multiple myeloma needs to be individualized. A patient with extensive lytic lesions or a spinal fracture should not begin an exercise or supplement program without discussing it with his or her oncology team.
I am a long-term survivor of multiple myeloma. My research and experience with evidence-based non-conventional therapies is the reason why I have lived in complete remission from my incurable blood cancer since achieving complete remission in early 1999. I have learned that the best way to manage cancer is to combine the best of conventional and evidence-based non-conventional therapies.
I have come to believe that therapy-induced side effects such as bone damage can be life-threatening while ruining quality of life. Consider therapies shown to reduce possible side effects.
Scroll down the page and post a question or a comment if there’s anything you’d like to know about bone health in multiple myeloma.
Good luck,
David Emerson
Possible MM Therapies-
- Radiation for Cancer: What Patients Need to Know
- Surgery for Cancer: What Patients Need to Know
- Immunotherapy for Cancer: What Patients Need to Know Before, During, and After Treatment
- Evidence-Based, Non-Conventional Multiple Myeloma Therapies: What Patients Should Know
- Dara-KRd for Multiple Myeloma: Side Effects, Integrative Therapies, and Recovery
Concepts Central to Managing Your Cancer-
- Integrative Oncology: Combining Conventional and Natural Cancer Therapies
- Complementary Cancer Therapies: Evidence-based
- Managing Cancer Treatment Side Effects: An Evidence-Based Guide to Prevention, Relief, and Recovery
- Cancer Financial Toxicity: Costs, Medical Debt, Insurance, Financial Assistance, and Survivorship
Why Bone Health Is So Important in Multiple Myeloma
Multiple myeloma develops in plasma cells within the bone marrow. Unfortunately, the disease can disrupt the normal process of bone remodeling.
Myeloma cells and the surrounding bone marrow environment can stimulate osteoclast activity—the cells responsible for breaking down bone—while suppressing osteoblast activity, which normally builds new bone.
The result can be:
- Osteolytic bone lesions
- Osteoporosis or osteopenia
- Bone pain
- Vertebral compression fractures
- Pathologic fractures
- Spinal instability
- Hypercalcemia
- Loss of mobility
- Reduced quality of life
Bone involvement is common in multiple myeloma. The International Myeloma Working Group recommends sensitive imaging techniques because detecting bone and bone-marrow lesions is important for diagnosis, treatment planning, and prevention of skeletal complications.
Multiple Myeloma Bone Health: The Essential PeopleBeatingCancer Articles
The following articles form a multiple myeloma bone-health library.
1. Multiple Myeloma Bone Health: Evidence-Based Ways to Reduce Bone Loss
This is the best starting point for understanding the big picture.
The article discusses:
- Bisphosphonates
- Denosumab
- Exercise
- Vitamin D
- Calcium
- Protein
- Nutrition
- Sleep
- Curcumin
- Vitamin K2
- Magnesium
- Other integrative approaches
It also explains why bone health needs to remain a priority for newly diagnosed patients and long-term survivors.
2. Myeloma and Your Bones: Diagnostics, Therapies and Dangers
This article focuses on the fundamentals of myeloma bone disease, including:
- Osteolytic lesions
- Bone pain
- Fractures
- Vertebral involvement
- Hypercalcemia
- Skeletal-related events
- Bisphosphonates
- Radiation
- Kyphoplasty
- Surgical intervention
Bone lesions most commonly involve the vertebrae, ribs, skull, pelvis and femur.
How Is Myeloma Bone Disease Diagnosed?
Bone health begins with knowing what is actually happening to the skeleton.
Traditional skeletal X-rays have increasingly been supplemented or replaced by more sensitive imaging.
Whole-Body Low-Dose CT
Whole-body low-dose CT can identify osteolytic lesions that may not be visible on conventional skeletal surveys.
The International Myeloma Working Group considers whole-body low-dose CT an important imaging modality for assessing bone disease.
MRI
MRI is particularly useful for detecting abnormalities involving the bone marrow and spine.
PET/CT
FDG-PET/CT can provide information about metabolically active myeloma lesions and is particularly useful in assessing treatment response.
Why This Matters
A patient experiencing persistent or unexplained bone pain should not necessarily assume that the pain is simply a consequence of aging or previous treatment.
The appropriate imaging study may reveal:
- A lytic lesion
- A compression fracture
- Active myeloma
- Osteoporosis
- Another cause of pain
Multiple Myeloma Bone Pain
Bone pain can be one of the most disruptive symptoms of myeloma.
Pain may result from:
- Osteolytic lesions
- Vertebral compression fractures
- Pathologic fractures
- Spinal instability
- Nerve compression
- Treatment-related damage
- Osteoporosis
- Previous radiation
Treatment therefore depends on why the bone hurts.
Pain management may involve:
- Treating the underlying myeloma
- Bone-modifying medications
- Analgesic medications
- Radiation therapy
- Physical therapy
- Bracing
- Vertebral augmentation
- Surgery in selected circumstances
- Complementary pain-management approaches
ASCO guidelines specifically recognize bone-modifying agents as part of managing pain associated with osteolytic disease and as adjuncts to radiation, analgesics and procedures for fractures or impending fractures.
What Are the Best Bone-Strengthening Drugs for Myeloma?
Two major categories of bone-modifying therapy are used in multiple myeloma:
Bisphosphonates
Commonly used medications include:
- Zoledronic acid
- Pamidronate
These drugs reduce osteoclast-mediated bone resorption.
Denosumab
Denosumab works differently. It targets RANKL, a key signal involved in osteoclast formation and activity.
Both approaches can reduce skeletal complications, but they have different considerations.
For example, kidney function is particularly important when considering intravenous bisphosphonates. ASCO recommends monitoring renal function with zoledronic acid or pamidronate and notes that denosumab does not require renal dose modification.
Patients should not choose between these medications based simply on which one sounds safer. Kidney function, disease status, fracture risk, dental health, calcium and vitamin D status, prior treatment and other factors matter.
Osteonecrosis of the Jaw: An Important Bone-Therapy Side Effect
One issue that every myeloma patient receiving a bone-modifying agent should understand is medication-related osteonecrosis of the jaw (MRONJ).
Bisphosphonates and denosumab have both been associated with MRONJ.
Good dental care and preventive oral-health practices can reduce risk.
Before beginning long-term bone-modifying therapy, patients should ask their oncology and dental teams:
- Do I need a dental examination?
- Are there teeth that should be treated first?
- Should invasive dental procedures be completed before treatment?
- How should dental procedures be handled after treatment begins?
What Happens When Multiple Myeloma Causes a Spinal Compression Fracture?
Vertebral compression fractures can cause severe pain and loss of mobility.
Treatment depends on the severity of the fracture, neurological symptoms, spinal stability, and the patient’s overall condition.
Potential approaches include:
- Pain medication
- Bracing
- Physical therapy
- Treatment of osteoporosis or underlying bone disease
- Vertebral augmentation
- Radiation in selected circumstances
- Surgery when instability or neurological compromise is present
When Is Radiation Used for Myeloma Bone Pain?
Radiation can be particularly useful when a localized bone lesion causes significant pain or threatens important structures.
The IMWG recommends radiotherapy for selected situations including:
- Uncontrolled pain
- Impending or symptomatic spinal cord compression
- Pathologic fractures
Radiation is therefore not simply a treatment for the myeloma itself. It can also be an important palliative bone therapy.
PeopleBeatingCancer also has an article examining the relationship between radiation and subsequent bone loss:
Myeloma, PEMF, Radiation Bone Loss
That article is particularly relevant to survivors who experienced radiation to bone and subsequently developed concerns about bone strength.
Can Exercise Help Multiple Myeloma Bone Health?
Exercise is an important part of myeloma survivorship—but the type of exercise matters.
Appropriately prescribed exercise can help support:
- Muscle strength
- Balance
- Mobility
- Physical function
- Bone health
- Cardiovascular health
- Fatigue management
- Quality of life
PeopleBeatingCancer’s Multiple Myeloma—Exercise collection discusses exercise before, during and after treatment and its potential effects on bone mineral density, fatigue and other aspects of survivorship.
However, patients with significant bone lesions, osteoporosis, fractures or spinal instability may need substantial modifications.
Do not assume that “weight-bearing exercise” means heavy lifting.
Walking, carefully prescribed resistance training, balance exercises and physical therapy may be more appropriate depending on the individual’s bone status.
Nutrition for Multiple Myeloma Bone Health
Bone is living tissue. Maintaining it requires adequate nutrition.
Important considerations include:
Protein
Muscle supports mobility and helps protect against falls. Adequate protein intake can therefore be part of a larger bone-health strategy.
Vitamin D
Vitamin D status should be monitored and deficiencies corrected when appropriate.
Calcium
Calcium is necessary for normal bone metabolism, but more is not necessarily better.
Patients receiving myeloma bone-modifying medications should discuss calcium intake and supplementation with their healthcare team.
Overall Diet
PeopleBeatingCancer’s Multiple Myeloma Diet collection explores nutrition, protein, fruits and vegetables, supplements and other dietary considerations for myeloma survivors.
Supplements and Myeloma Bone Health
Patients frequently ask whether supplements can strengthen bones damaged by myeloma.
Some nutrients are biologically important to bone metabolism, including:
- Vitamin D
- Calcium
- Magnesium
- Vitamin K
- Protein
But supplements deserve the same level of scrutiny as medications.
Potential problems include:
- Excessive dosing
- Drug interactions
- Kidney problems
- Hypercalcemia
- Contamination
- Lack of evidence in human myeloma patients
PeopleBeatingCancer’s Multiple Myeloma Supplements for Better Health provides a broader discussion of supplements and supportive care.
My recommendation: don’t assume that a supplement is safe simply because it is natural.
Bone Health After Myeloma Treatment
Bone health does not necessarily become unimportant once active myeloma treatment ends.
Long-term survivors may have several overlapping risks:
- Previous bone lesions
- Previous fractures
- Osteoporosis
- Long-term corticosteroid exposure
- Reduced physical activity
- Loss of muscle mass
- Treatment-related complications
- Previous radiation
- Aging
That means bone health should become part of long-term survivorship, not simply something discussed during induction therapy.
Myeloma Bone Health: Questions to Ask Your Oncologist
Consider taking this checklist to your next appointment:
- Do I have any lytic bone lesions?
- Where are my bone lesions located?
- Do I have osteoporosis or osteopenia?
- Have I had a vertebral compression fracture?
- What imaging should I have to monitor my bone disease?
- Should I receive a bisphosphonate?
- Is denosumab appropriate for me?
- How is my kidney function affecting my bone-treatment options?
- How long should I receive bone-modifying therapy?
- Do I need a dental examination before treatment?
- What is my risk of osteonecrosis of the jaw?
- Should I have my vitamin D level checked?
- How much calcium should I obtain from food and supplements?
- What types of exercise are safe for me?
- Should I work with a physical therapist?
- What should I do if I develop new bone pain?
- What symptoms could indicate a fracture or spinal cord compression?
Myeloma Bone Health: The PeopleBeatingCancer Approach
Myeloma patients often focus understandably on the medications being used to control the cancer.
Bone health deserves equal attention.
A comprehensive approach may include:
Control the myeloma
↓
Assess bone damage
↓
Prevent skeletal complications
↓
Treat bone pain
↓
Protect bone density
↓
Preserve muscle and mobility
↓
Reduce fall and fracture risk
↓
Maintain bone health during survivorship
The objective isn’t simply to make a scan look better.
The objective is to help the patient remain mobile, independent, and functional for as long as possible.
PeopleBeatingCancer’s Myeloma Bone Health Library
For patients and caregivers who want to go deeper, these are particularly relevant PeopleBeatingCancer articles:
- Multiple Myeloma Bone Health: Evidence-Based Ways to Reduce Bone Loss
- Myeloma and Your Bones—Diagnostics, Therapies and Dangers
- Multiple Myeloma—Need to Know
- Steroid-Induced Avascular Necrosis
- Multiple Myeloma Side Effect—Osteonecrosis of the Jaw Prevention
- Cancer Survivors—Managing Chronic Non-Cancer Pain
- Multiple Myeloma Side Effects—Acupuncture for Pain
- Multiple Myeloma Vitamin D Deficiency
- Multiple Myeloma Diet- Foods for Survivors to Avoid
- Supplement During Myeloma Treatment?
- Multiple Myeloma—Prehabilitation
- Neuropathic Pain Care
Together, these articles create a much larger picture than any single article can provide.
The Bottom Line
Bone health is a lifelong issue for many people living with multiple myeloma.
Myeloma can weaken bone. Treatment can affect bone and muscle. Steroids can contribute to bone loss. Radiation can affect treated bone. Fractures can permanently affect mobility and independence.
But patients have more tools than they once did.
Bone-modifying medications, sensitive imaging, radiation, vertebral procedures, surgery when necessary, exercise, nutrition, physical therapy and careful survivorship management can all play a role.
The most important step is to make bone health an explicit part of your multiple myeloma treatment and survivorship plan.
Evidence Rating
PeopleBeatingCancer Evidence Rating:
| Approach | Evidence for Myeloma Bone Health | My Take |
|---|---|---|
| Zoledronic acid / pamidronate | ★★★★★ | Strong evidence; standard supportive care |
| Denosumab | ★★★★★ | Strong evidence; important alternative |
| Dental prevention with bone-modifying therapy | ★★★★★ | Strongly recommended |
| Radiation for selected painful bone disease | ★★★★★ | Established palliative treatment |
| Vertebral augmentation for selected painful fractures | ★★★★☆ | Evidence supports selected patients |
| Exercise | ★★★★☆ | Important, but must be individualized |
| Adequate vitamin D | ★★★★☆ | Correct deficiency; avoid megadosing |
| Adequate calcium | ★★★★☆ | Important, but individualized |
| Physical therapy | ★★★★☆ | Particularly useful for mobility/function |
| Magnesium/K2/other supplements | ★★☆☆☆ | Evidence is much less certain in myeloma |
A critical distinction: evidence that a nutrient or supplement supports normal bone biology is not the same as evidence that it treats myeloma bone disease. Patients should keep those claims separate.
Research
- ASCO Clinical Practice Guideline—Bone-Modifying Agents in Multiple Myeloma
Anderson KC, et al. J Clin Oncol. Bone-modifying agents, bisphosphonates, denosumab, renal monitoring, duration and pain management. - International Myeloma Working Group—Treatment of Myeloma-Related Bone Disease
Terpos E, et al. Lancet Oncology. Bone-modifying therapy, vertebral augmentation, radiotherapy and surgical indications. - International Myeloma Working Group—Imaging Recommendations
Whole-body low-dose CT, MRI and PET/CT for assessment of myeloma bone and marrow disease. - MASCC/ISOO/ASCO Guideline—Medication-Related Osteonecrosis of the Jaw
Prevention and management of osteonecrosis associated with bisphosphonates and denosumab. - ASCO Living Guideline—Treatment of Multiple Myeloma, Version 2026.1.2
The current living ASCO guideline for multiple myeloma treatment, updated June 26, 2026.