

Our Mission
PeopleBeatingCancer supports an evidence-based integrative approach to cancer care. For most newly diagnosed patients, FDA-approved therapies form the foundation of treatment, while evidence-based complementary therapies may help reduce side effects and improve survivorship.
Click the orange button to the right to learn more.
- You are here:
- Home »
- Blog »
- breast cancer »
- Life After Breast Cancer: Long-Term Side Effects and Survivorship
Life After Breast Cancer: Long-Term Side Effects and Survivorship
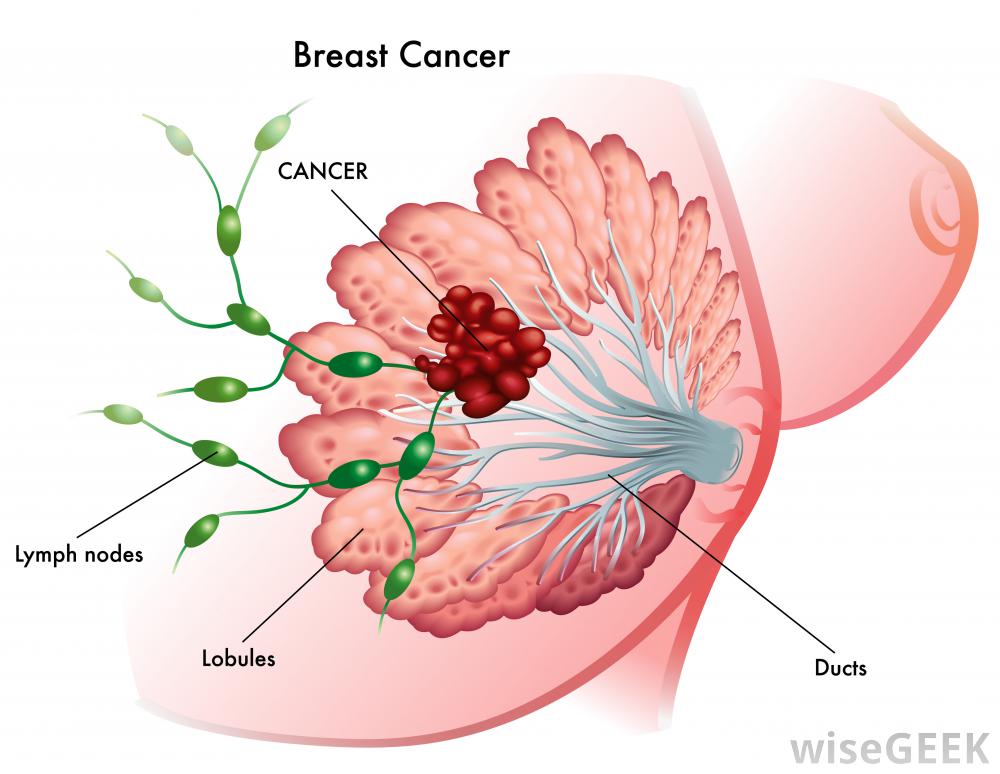

Life After Breast Cancer: Long-Term Side Effects and Survivorship. Breast cancer treatment can save your life—but finishing treatment does not necessarily mean that the effects of breast cancer treatment are finished.
Some breast cancer survivors experience fatigue, pain, neuropathy, cognitive problems, sleep disturbances, hormonal changes, sexual problems, lymphedema, bone loss, cardiovascular problems, anxiety, depression, or other health problems for months or years after treatment.
Some Life After Breast Cancer problems begin during treatment and persist. Others are late effects, meaning they develop months or years after treatment has ended.
The National Cancer Institute (NCI) notes that late effects can occur long after cancer treatment and may involve the heart, lungs, bones, nervous system, reproductive system, and other organs.
The important message for breast cancer survivors is this:
Persistent symptoms after breast cancer treatment should not simply be accepted as the price of survival. Many long-term and late effects can be evaluated, treated, or managed.
I am a long-term survivor of an incurable blood cancer called multiple myeloma. My long-term and late-stage side effects are similar to the list discussed below. At this point in my life as a cancer survivor, the risk of my dying from a side effect such as chemotherapy-induced cardiomyopathy is greater than my dying from my original cancer,
The purpose in writing this post on PeopleBeatingCancer.org is to prepare Breast Cancer patients- first about the basics of breast cancer and second about possible long-term and late-stage side effects of breast cancer treatments. It is my experience that most oncologists spend little time educating their patients about side effect prevention.
Further, evidence-based, non-conventional therapies such as Prehabilitation and Gut Microbiome Health can reduce the risk of side effects.
My research and experience with evidence-based non-conventional therapies is the reason why I have lived in complete remission from my incurable blood cancer since achieving complete remission in early 1999. I have learned that the best way to manage cancer is to combine the best of conventional and evidence-based non-conventional therapies.
I have come to believe that therapy-induced side effects can be life-threatening while ruining quality of life. Consider therapies shown to reduce possible side effects.
Scroll down the page and post a question or a comment if there’s anything you’d like to know about breast cancer.
Good luck,
David Emerson
Concepts Central to Managing Your Cancer
- Integrative Oncology: Combining Conventional and Natural Cancer Therapies
- Complementary Cancer Therapies: Evidence-based
- Managing Cancer Treatment Side Effects: An Evidence-Based Guide to Prevention, Relief, and Recovery
- Breast Cancer and Pain: What Patients and Survivors Need to Know
- Breast Cancer and Financial Toxicity: What Patients Need to Know
Possible Breast Cancer Therapies
- Radiation for Breast Cancer: What Patients Need to Know
- Breast Cancer Surgery: What Patients Need to Know
- Chemotherapy for Breast Cancer: What Patients Need to Know
- Immunotherapy for Cancer: What Patients Need to Know Before, During, and After Treatment
- AC Chemotherapy (Adriamycin + Cyclophosphamide): What Patients Need to Know
What Are Long-Term and Late Effects of Breast Cancer Treatment?
There is an important distinction.
Long-term effects generally begin during cancer treatment and continue after treatment ends.
Late effects may not become apparent until months or years after treatment.
For example:
- Chemotherapy-related peripheral neuropathy may continue for years.
- Lymphedema may develop long after lymph-node surgery or radiation.
- Hormone therapy may contribute to long-term joint symptoms and bone loss.
- Radiation involving the chest can increase the risk of later heart and lung problems.
- Fatigue, anxiety, depression, cognitive problems, and insomnia may persist after treatment has ended.
Not every breast cancer survivor develops these problems. Risk depends on the individual’s cancer, treatment history, age, genetics, other medical conditions, and lifestyle.
1. Chronic Fatigue After Breast Cancer
Fatigue is one of the most common and potentially disabling long-term problems reported by cancer survivors.
Cancer-related fatigue is different from ordinary tiredness. It may not disappear after sleeping or resting and can interfere with work, exercise, relationships, and daily activities.
The 2024 ASCO–Society for Integrative Oncology guideline reports that approximately 20%–30% of cancer survivors continue to experience clinically significant fatigue for months or years after treatment. The causes are often multifactorial and may include physical deconditioning, pain, sleep problems, depression, anxiety, anemia, nutritional problems, medication effects, and the effects of cancer treatment itself.
Evidence-based treatments for cancer-related fatigue
The strongest evidence supports:
- Aerobic exercise
- Resistance training
- Combined aerobic and resistance exercise
- Cognitive behavioral therapy (CBT)
- Mindfulness-based programs
ASCO recommends exercise, CBT, and mindfulness-based programs for cancer survivors with persistent cancer-related fatigue. Yoga, acupressure, and moxibustion may also be considered.
Exercise does not have to mean strenuous exercise. A supervised program can begin with walking, light resistance training, physical therapy, or other activity appropriate for the survivor’s fitness and medical condition.
Important
Persistent fatigue deserves a medical evaluation rather than simply being attributed to “having had cancer.”
A clinician may need to evaluate anemia, thyroid dysfunction, depression, anxiety, sleep apnea, medication effects, pain, nutritional deficiencies, cardiovascular disease, or cancer recurrence.
2. Cancer-Related Cognitive Impairment (“Chemo Brain”)
Some breast cancer survivors describe problems with:
- Memory
- Concentration
- Finding words
- Multitasking
- Processing information
- Attention
- Mental fatigue
- Executive function
The term “chemo brain” is commonly used, although cognitive problems can occur in people who did not receive chemotherapy and may involve multiple factors, including endocrine therapy, fatigue, sleep disturbance, anxiety, depression, inflammation, and the cancer experience itself.
Research has documented cognitive problems among breast cancer survivors, and recent systematic reviews have found that exercise can improve several cognitive domains.
A 2025 meta-analysis of randomized trials involving 890 breast cancer survivors found that exercise improved attention and working memory, executive function, perceived cognitive abilities, and cognitive complaints.
Another 2024 network meta-analysis of 34 randomized trials found benefits from exercise and mindfulness-based interventions for cognitive impairment, with physical activity and qigong showing benefits for executive function.
Evidence-based approaches
Potentially helpful interventions include:
- Regular aerobic exercise
- Resistance training
- Mind-body exercise
- Cognitive rehabilitation
- Compensatory cognitive training
- Mindfulness-based programs
Cognitive training is an emerging intervention. A 2025 systematic review and meta-analysis found a statistically significant, although relatively modest, improvement in cognitive outcomes with cognitive training.
Practical strategy
A survivor with significant cognitive problems may benefit from an occupational therapist, neuropsychologist, or cancer rehabilitation program rather than simply being told to “try harder to concentrate.”
3. Insomnia and Sleep Problems
Sleep disturbances can become chronic after breast cancer treatment.
Insomnia can also create a vicious cycle:
poor sleep → fatigue → reduced activity → depression/anxiety → worse sleep.
A meta-analysis of 14 randomized trials involving 1,363 people with breast cancer found that cognitive behavioral therapy for insomnia (CBT-I) significantly improved insomnia and sleep quality, with benefits persisting at 12 months.
More broadly, a 2024 systematic review and meta-analysis involving 61 randomized trials found CBT-I to be the most efficacious intervention studied for insomnia in cancer survivors.
Best-supported treatment
CBT-I should be considered a first-line treatment for chronic insomnia.
CBT-I typically addresses:
- Sleep scheduling
- Stimulus control
- Sleep-related behaviors
- Cognitive beliefs about sleep
- Relaxation
- Sleep hygiene
Exercise, mindfulness, relaxation techniques, and other mind-body interventions may provide additional benefit.
4. Depression, Anxiety and Fear of Recurrence
Completing breast cancer treatment does not necessarily end the emotional consequences of cancer.
Survivors may experience:
- Depression
- Generalized anxiety
- Panic
- Post-traumatic stress symptoms
- Fear of recurrence
- Uncertainty about the future
- Loss of confidence in their body
- Social isolation
These symptoms may be especially noticeable when frequent medical appointments end and the survivor is expected to “return to normal.”
Evidence-based treatments
Treatment should be individualized and can include:
- Psychotherapy
- Cognitive behavioral therapy
- Mindfulness-based stress reduction
- Exercise
- Support groups
- Antidepressant or anti-anxiety medication when clinically appropriate
Recent systematic reviews of breast cancer research have found evidence that CBT can reduce anxiety and depression symptoms.
A 2025 meta-analysis of mindfulness interventions also found significant reductions in anxiety and depression among people with breast cancer.
5. Lymphedema
Breast cancer-related lymphedema can occur after:
- Sentinel lymph-node procedures
- Axillary lymph-node dissection
- Radiation therapy
- Other damage to the lymphatic system
Importantly, lymphedema can appear months or years after treatment.
Symptoms may include:
- Swelling of the arm or hand
- Heaviness
- Tightness
- Reduced range of motion
- Skin changes
- Recurrent infections
Evidence-based management
Treatment may involve a certified lymphedema therapist and can include:
- Compression garments
- Exercise
- Skin care
- Manual lymphatic techniques
- Complete decongestive therapy
- Pneumatic compression in selected patients
Exercise is no longer considered something that breast cancer survivors with lymphedema should automatically avoid.
Systematic reviews have found that progressive resistance exercise can be performed safely and can improve strength without necessarily worsening lymphedema.
A 2025 umbrella review and meta-analysis also found strong evidence that exercise improves strength and upper-limb disability among people at risk for or living with breast cancer-related lymphedema.
Exercise should be progressed gradually and individualized, particularly in someone with established lymphedema.
6. Peripheral Neuropathy
Some chemotherapy drugs can damage peripheral nerves.
Symptoms can include:
- Numbness
- Tingling
- Burning
- Electric-shock sensations
- Loss of balance
- Sensitivity to touch
- Difficulty walking
- Problems using the hands
Neuropathy does not always disappear when chemotherapy ends.
One study of 1,031 women treated with docetaxel for early-stage breast cancer found that among those who developed grade 2–4 peripheral neuropathy during treatment, approximately one-third continued to have significant neuropathy 1–3 years later.
Management
Management may include:
- Physical therapy
- Balance training
- Exercise
- Occupational therapy
- Fall prevention
- Pain management
- Selected medications for neuropathic pain
Importantly, acetyl-L-carnitine should not be routinely recommended to prevent chemotherapy-induced peripheral neuropathy; ASCO/SIO guidance has identified potential harm.
7. Joint and Muscle Pain From Hormone Therapy
Aromatase inhibitors—including anastrozole, letrozole and exemestane—are highly effective treatments for many hormone-receptor-positive breast cancers.
But they can cause persistent:
- Joint pain
- Muscle pain
- Stiffness
- Reduced physical activity
These symptoms can become an important reason women discontinue endocrine therapy.
Evidence-based management
Options include:
- Exercise
- Physical therapy
- Weight management when appropriate
- Analgesic medications
- Acupuncture
- Switching endocrine therapies under medical supervision
Systematic reviews and network meta-analyses have found evidence supporting exercise and acupuncture for aromatase-inhibitor-associated arthralgia.
One important point:
Do not stop an aromatase inhibitor or tamoxifen because of side effects without discussing alternatives with the oncology team.
Changing medications, taking a medically appropriate break, or switching to another endocrine therapy may sometimes allow a survivor to continue effective treatment.
8. Menopause, Hot Flashes and Hormonal Changes
Breast cancer treatment can produce or accelerate menopause.
Symptoms may include:
- Hot flashes
- Night sweats
- Vaginal dryness
- Sleep disruption
- Mood changes
- Reduced libido
- Pain with intercourse
- Urinary symptoms
For women with hormone-sensitive breast cancer, treatment of menopausal symptoms can be more complicated because systemic estrogen therapy may not be appropriate.
Nonhormonal treatment options
Evidence supports several approaches, depending on the individual:
- Venlafaxine
- Certain SSRIs/SNRIs
- Gabapentin
- Acupuncture
- Behavioral interventions
- Cooling and lifestyle strategies
A systematic review of randomized trials found evidence for venlafaxine, gabapentin and several other nonhormonal approaches to hot flashes in breast cancer survivors.
Medication choice is particularly important for women taking tamoxifen, because some medications can interfere with CYP2D6 metabolism and potentially affect tamoxifen activation.
9. Sexual Health After Breast Cancer
Sexual problems are common but frequently underdiagnosed.
Potential problems include:
- Loss of libido
- Vaginal dryness
- Pain with intercourse
- Difficulty becoming aroused
- Changes in orgasm
- Body-image concerns
- Fear of intimacy
A systematic review found that sexual dysfunction is common among breast cancer survivors and that vaginal moisturizers, counseling, education and other targeted interventions can help some women, although the evidence base remains heterogeneous.
Management may include
- Vaginal moisturizers
- Lubricants
- Pelvic-floor physical therapy
- Sexual counseling
- Couples counseling
- Psychotherapy
- Medical evaluation of genitourinary symptoms
Hormonal vaginal treatments require individualized discussion with the oncology team, particularly in women with estrogen-receptor-positive disease.
10. Bone Loss and Osteoporosis
Breast cancer treatment can affect bone health.
Risk can increase with:
- Aromatase inhibitors
- Ovarian suppression
- Premature menopause
- Certain chemotherapy regimens
- Radiation involving bone
- Reduced physical activity
NCI identifies chemotherapy, hormonal therapy and radiation as potential contributors to bone loss.
Evidence-based prevention and treatment
Bone health management may include:
- Baseline and follow-up bone-density testing
- Weight-bearing exercise
- Resistance training
- Adequate calcium intake
- Adequate vitamin D
- Smoking cessation
- Limiting excessive alcohol
- Bisphosphonates when indicated
- Denosumab when indicated
Current breast cancer follow-up guidance emphasizes monitoring bone mineral density in women receiving endocrine therapy and appropriate use of antiresorptive therapy when indicated.
This is an area where prevention is particularly important, because a fracture can permanently affect mobility and independence.
11. Heart Disease After Breast Cancer Treatment
One of the most important late effects is cardiovascular disease.
Certain breast cancer treatments can affect the heart, including:
- Doxorubicin and other anthracyclines
- Trastuzumab
- Chest radiation
- Some other systemic treatments
The NCI notes that some treatment-related heart problems may not appear until years after treatment. These can include weakening of the heart muscle and coronary artery disease.
Radiation therapy for breast cancer can also produce late heart effects depending on the radiation field and dose.
Survivorship management
A breast cancer survivor should know her cardiovascular risk factors, including:
- Blood pressure
- Cholesterol
- Diabetes
- Smoking
- Weight
- Physical activity
- Family history
Exercise, smoking cessation, blood-pressure control, diabetes management, lipid management and appropriate cardiovascular follow-up are important components of survivorship care.
Some survivors may benefit from referral to cardio-oncology or cardiac rehabilitation.
12. Lung Problems After Breast Cancer Radiation
Radiation involving the chest can sometimes produce long-term pulmonary effects.
Potential problems include:
- Radiation pneumonitis
- Pulmonary fibrosis
- Shortness of breath
- Reduced exercise tolerance
NCI identifies lung problems among the possible late effects of breast radiation.
Persistent or worsening shortness of breath should not automatically be attributed to aging or deconditioning.
A physician may need to evaluate the heart, lungs, anemia, medications and—when appropriate—possible cancer recurrence.
13. Chronic Pain
Persistent pain can originate from several sources:
- Surgery
- Nerve injury
- Radiation
- Neuropathy
- Musculoskeletal changes
- Aromatase inhibitors
- Scar tissue
- Lymphedema
The best treatment depends on the cause.
Potential approaches include:
- Physical therapy
- Exercise
- Occupational therapy
- Acupuncture
- Neuropathic pain medications
- Non-opioid analgesics
- Psychological interventions
- Pain-management specialists
A multidisciplinary approach is often more useful than simply increasing pain medication.
14. Body Image and Physical Changes
Mastectomy, lumpectomy, reconstruction, radiation, scars, hair loss, weight changes and premature menopause can permanently alter the way a woman sees her body.
Body-image concerns can affect:
- Self-esteem
- Sexuality
- Intimacy
- Clothing choices
- Exercise
- Social relationships
Counseling, peer support, sexual-health counseling, physical rehabilitation, and reconstructive surgery when appropriate can all be part of survivorship care.
These problems are not superficial.
Body image is part of quality of life.
15. Second Cancers
Some cancer treatments can slightly increase the risk of developing another cancer later.
Radiation therapy is one example. NCI notes that breast radiation can rarely contribute to second cancers, while also identifying heart, lung, bone and lymphatic complications as potential late effects.
The absolute risk varies considerably depending on the radiation field, dose, age at treatment and other factors.
This is one reason long-term follow-up remains important even when breast cancer is considered successfully treated.
16. What Can Breast Cancer Survivors Do to Reduce Long-Term Problems?
There is no single “breast cancer survivorship diet” or supplement that prevents every late effect.
Instead, the evidence increasingly supports a multidimensional survivorship strategy.
1. Exercise
Exercise is one of the most consistently supported interventions in cancer survivorship.
It can help with:
- Fatigue
- Physical function
- Anxiety
- Depression
- Sleep
- Bone health
- Muscle strength
- Cardiovascular fitness
- Cognitive function
- Quality of life
ASCO guidance supports individualized aerobic and resistance exercise for cancer survivors.
2. Maintain a healthy body weight
Weight management can be particularly important after breast cancer because excess body weight is associated with multiple adverse health outcomes.
However, the goal should be sustainable nutrition and physical activity rather than extreme dieting.
3. Don’t smoke
Smoking increases cardiovascular disease and cancer risk and can compound some late effects of cancer treatment.
4. Limit excessive alcohol
Alcohol can increase breast cancer risk and may also contribute to osteoporosis, cardiovascular disease and other health problems.
5. Treat sleep problems
Do not simply accept chronic insomnia.
CBT-I has some of the strongest evidence available for cancer-related insomnia.
6. Treat depression and anxiety
Psychological health is part of physical survivorship—not something separate from it.
7. Maintain bone health
Ask whether you need:
- Bone-density testing
- Vitamin D assessment
- Calcium assessment
- Weight-bearing exercise
- Antiresorptive treatment
8. Protect cardiovascular health
Know your:
- Blood pressure
- Cholesterol
- Blood sugar
- Weight
- Physical activity level
And tell your primary-care physician about your breast cancer treatment history.
17. What About Integrative Therapies?
There is growing evidence for selected integrative approaches, but breast cancer survivors should distinguish between evidence-supported supportive care and therapies marketed as cancer treatments.
Evidence-supported or potentially useful approaches include:
- Exercise
- Yoga
- Mindfulness
- CBT
- CBT-I
- Acupuncture
- Qigong
- Tai chi
- Rehabilitation
- Massage/physical therapy in selected circumstances
For example, a meta-analysis of acupuncture trials involving more than 2,000 breast cancer patients found improvements in pain, fatigue and hot flashes compared with control groups.
However, “natural” does not automatically mean safe.
Supplements can interact with endocrine therapies, chemotherapy, anticoagulants and other medications.
ASCO/SIO’s fatigue guideline found that many dietary supplements do not have convincing evidence for persistent cancer-related fatigue.
18. When Should a Breast Cancer Survivor Seek Medical Attention?
Persistent symptoms deserve evaluation, especially when they are new, worsening or interfering with daily life.
Contact your healthcare team about:
- New or worsening fatigue
- Persistent shortness of breath
- Chest pain
- New swelling of an arm or breast
- Persistent or worsening pain
- New neurologic symptoms
- Significant cognitive changes
- Depression or anxiety
- Persistent insomnia
- New bone pain
- Unexplained weight loss
- New lumps or swelling
- New headaches or neurologic symptoms
These symptoms do not necessarily mean that breast cancer has returned.
But they deserve appropriate evaluation.
19. The Breast Cancer Survivorship Checklist
A useful survivorship visit should consider more than mammography.
Ask your healthcare team about:
Physical health
-
Fatigue
-
Pain
-
Neuropathy
-
Lymphedema
-
Exercise capacity
-
Blood pressure
-
Cardiovascular risk
-
Bone health
Brain and mental health
-
Memory
-
Concentration
-
Sleep
-
Anxiety
-
Depression
-
Fear of recurrence
Hormonal health
-
Menopause
-
Hot flashes
-
Vaginal symptoms
-
Sexual health
-
Endocrine therapy side effects
Lifestyle
-
Physical activity
-
Nutrition
-
Weight management
-
Alcohol
-
Tobacco
-
Social connection
Cancer surveillance
-
Breast imaging as recommended
-
Clinical follow-up
-
Monitoring for treatment-related complications
-
Evaluation of new symptoms
20. The Goal of Survivorship Is More Than “No Evidence of Disease”
For many breast cancer survivors, the end of treatment creates a strange transition.
The cancer may no longer be detectable, but the consequences of treatment may remain.
That means survivorship should not simply mean:
“Your treatment is over. See you next year.”
It should mean:
“How are you functioning? How do you feel? What problems remain? What can we do about them?”
The growing field of cancer survivorship recognizes that quality of life, cardiovascular health, bone health, cognitive function, mental health, physical function and sexual health are all legitimate parts of cancer care.
And many of these problems are treatable.
PeopleBeatingCancer Evidence Rating
Overall evidence for the existence of long-term and late effects after breast cancer treatment: HIGH
There is extensive evidence documenting persistent fatigue, cognitive impairment, sleep problems, lymphedema, neuropathy, endocrine symptoms, bone loss, cardiovascular effects and psychological consequences following breast cancer treatment.
Evidence for exercise as a broad survivorship intervention: HIGH
Exercise has evidence across multiple outcomes, including fatigue, physical function, mood, cardiovascular fitness, bone health and cognitive function.
Evidence for CBT/CBT-I: HIGH
CBT and CBT-I have substantial evidence for fatigue, insomnia, anxiety, depression and related survivorship symptoms.
Evidence for acupuncture: MODERATE
Evidence supports acupuncture for selected symptoms—including aromatase-inhibitor-associated joint pain, hot flashes and some treatment-related symptoms—but results vary by condition and study quality.
Evidence for dietary supplements as a general strategy for late effects: LOW/INSUFFICIENT
Individual supplements require individual evidence. Survivors should not assume that a supplement is safe or effective simply because it is marketed as “natural.”
Research and Evidence Sources
Long-term and late effects
National Cancer Institute — Late Effects of Cancer Treatment
NCI: Coping With Late Effects
NCI — Radiation Therapy for Breast Cancer
This resource documents potential late effects including heart and lung problems, bone weakness, lymphedema and rare second cancers.
ASCO — Long-Term Follow-Up Care After Treatment for Primary Breast Cancer
ASCO: Long-Term Follow-Up Care After Treatment for Primary Breast Cancer
Fatigue
ASCO–Society for Integrative Oncology Guideline: Management of Fatigue in Adult Cancer Survivors
PubMed: ASCO-SIO Fatigue Guideline
Cognitive impairment
Exercise and Cognitive Function in Breast Cancer Survivors — 2025 Meta-analysis
PubMed: Exercise and Cognitive Function
Exercise and Mindfulness for Cognitive Impairment — 2024 Network Meta-analysis
PubMed: Cognitive Impairment Interventions
Insomnia
CBT-I in Breast Cancer — Meta-analysis
PubMed: CBT-I in Breast Cancer
CBT-I in Cancer Survivors — Systematic Review and Meta-analysis
PubMed: CBT-I in Cancer Survivors
Lymphedema
Exercise and Breast Cancer-Related Lymphedema — Systematic Review
PubMed: Exercise and Breast Cancer-Related Lymphedema
Resistance Exercise and Breast Cancer-Related Lymphedema
PubMed: Resistance Exercise and Lymphedema
Neuropathy
Persistence of Docetaxel-Induced Neuropathy in Breast Cancer Survivors
PubMed: Persistent Docetaxel Neuropathy
Aromatase-inhibitor joint pain
Acupuncture for Aromatase-Inhibitor Arthralgia — Systematic Review and Meta-analysis
PubMed: Acupuncture for Aromatase-Inhibitor Arthralgia
Therapeutic Options for Aromatase-Inhibitor Arthralgia
PubMed: Treatment of Aromatase-Inhibitor Arthralgia
Sexual health
Management of Sexual Dysfunction in Breast Cancer Survivors — Systematic Review
PubMed: Sexual Dysfunction After Breast Cancer
Mental health
CBT for Depression and Anxiety in Breast Cancer — Systematic Review
PubMed: CBT for Depression and Anxiety in Breast Cancer
Integrative therapies
Acupuncture for Treatment-Related Symptoms in Breast Cancer Survivors — Systematic Review and Meta-analysis
PubMed: Acupuncture in Breast Cancer Survivors
Life After Breast Cancer Life After Breast Cancer Life After Breast Cancer Life After Breast Cancer Life After Breast Cancer Life After Breast Cancer Life After Breast Cancer Life After Breast Cancer