

Our Mission
PeopleBeatingCancer supports an evidence-based integrative approach to cancer care. For most newly diagnosed patients, FDA-approved therapies form the foundation of treatment, while evidence-based complementary therapies may help reduce side effects and improve survivorship.
Click the orange button to the right to learn more.
- You are here:
- Home »
- Blog »
- pediatric cancer »
- Pediatric Cancer: Reducing Treatment Side Effects and Long-Term Health Risks.
Pediatric Cancer: Reducing Treatment Side Effects and Long-Term Health Risks.
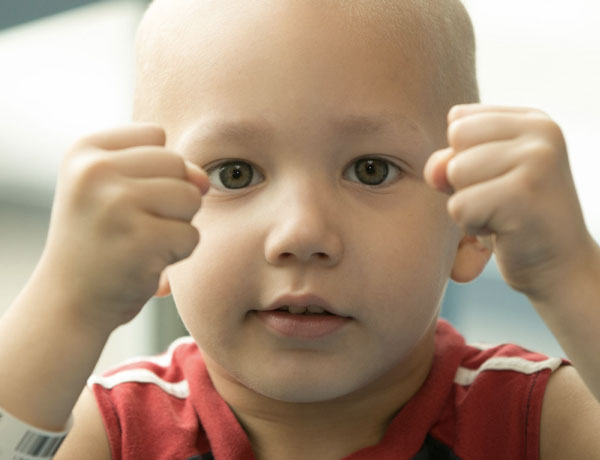

Pediatric Cancer: Reducing Treatment Side Effects and Long-Term Health Risks. Evidence-Based Conventional and Integrative Therapies for Children, Adolescents, and Childhood Cancer Survivors
What Parents and Survivors Need to Know
More than 85% of children diagnosed with cancer now survive at least five years. This represents one of the greatest achievements in modern oncology. However, surviving cancer does not necessarily mean escaping the long-term effects of treatment.
Chemotherapy, radiation therapy, surgery, corticosteroids, and stem cell transplantation can cause health problems that emerge months, years, or even decades after treatment ends.
These problems may include:
- Cardiomyopathy and heart failure
- Cognitive impairment and learning difficulties
- Peripheral neuropathy
- Hearing loss
- Osteoporosis and osteonecrosis
- Hormonal and reproductive problems
- Chronic fatigue and reduced physical functioning
- Secondary cancers
- Anxiety, depression, and other psychological challenges
The good news is that some complications can be prevented or reduced, many can be detected earlier, and others can be managed through conventional medical care, rehabilitation, nutrition, physical activity, and carefully selected complementary therapies.
The goal is not simply to cure childhood cancer. It is to help children survive and enjoy the healthiest possible adulthood.
I am both a long-term cancer survivor and parent. As a parent, I would admit that I would do most anything to treat my child’s cancer. As a long-term cancer survivor, I would do most anything to spare my child the lifetime of long-term and late-stage side effects that I have experienced.
Are you the caregiver of a child or AYA patient who has recently been diagnosed with cancer? Scroll down the page and tell me what’s on your mind.
Hang in there,
David Emerson
- Cancer Survivor
- Cancer Coach
- Director PeopleBeatingCancer
- To learn more about Heart disease after childhood cancer: Childhood and AYA survivor heart disease
- To learn more about Long-term risks for AYA survivors: Cardiovascular late effects and prevention
- To learn more about Managing Treatment Side Effects
- To learn how to Stay Healthy During Chemotherapy
Why Childhood Cancer Survivors Face Long-Term Health Risks
Children are still growing when they receive cancer treatment. Chemotherapy and radiation can affect developing organs, bones, the nervous system, reproductive tissues, and cardiovascular function. Some treatment-related injuries become apparent during therapy. Others remain undetected for years. A large Childhood Cancer Survivor Study analysis published in 2025 examined more than 15,000 survivors.
By age 35, the estimated risk of developing a severe chronic condition was:
| Survivor group | Risk by age 35 |
|---|---|
| Lower treatment-exposure risk | 11.9% |
| Medium risk | 15.1% |
| Higher risk | 25.4% |
| Sibling comparison group | 6.9% |
These results demonstrate an important point: not every childhood cancer survivor faces the same future.
The type of cancer, specific drugs, cumulative doses, radiation fields, age at treatment, genetic susceptibility, and subsequent health habits all influence risk.
Research: Treatment Exposure-Based Risk Stratification for Childhood Cancer Survivors
The Most Common Long-Term and Late Effects of Pediatric Cancer Treatment
1. Heart Damage and Cardiomyopathy
Anthracycline chemotherapy, including doxorubicin and daunorubicin, can injure heart muscle cells. Radiation involving the heart can also damage blood vessels, heart valves, and other cardiac structures.
Potential consequences include:
- Reduced left ventricular ejection fraction
- Cardiomyopathy
- Heart failure
- Coronary artery disease
- Valvular disease
- Abnormal heart rhythms
Some survivors develop symptoms decades after treatment.
Conventional prevention and management
Before and during treatment, pediatric oncologists may consider treatment modifications, cardioprotective strategies such as dexrazoxane when indicated, and appropriate cardiac monitoring. After treatment, survivors with relevant exposures should receive risk-based cardiovascular surveillance. Echocardiography, blood pressure management, and treatment of emerging cardiovascular disease can be important components of care.
Complementary approaches
Regular physical activity, nutritious eating, tobacco avoidance, and maintenance of healthy blood pressure can support cardiovascular health. However, these strategies have not been proven to eliminate anthracycline-induced cardiac damage.
For a more detailed discussion, read:
Childhood and AYA Cancer Survivors: Future Risk of Heart Disease
2. Cognitive Impairment and Learning Difficulties
Childhood cancer survivors may experience problems with:
- Memory
- Attention
- Processing speed
- Executive functioning
- Academic performance
These problems are particularly important after central nervous system tumors, cranial radiation, and certain intensive treatment regimens.
Conventional interventions
Neuropsychological testing, school accommodations, occupational therapy, cognitive rehabilitation, and individualized educational support may improve functioning.
Complementary interventions
Appropriate physical activity, sleep optimization, and stress-management practices may support cognitive and emotional well-being.
Evidence that nutritional supplements prevent treatment-related cognitive impairment in children remains insufficient.
3. Peripheral Neuropathy
Vincristine, platinum chemotherapy, and other neurotoxic treatments can damage peripheral nerves.
Symptoms may include:
- Tingling and numbness
- Burning pain
- Weakness
- Poor balance
- Difficulty walking
Some symptoms improve after treatment. Others persist into adulthood.
Conventional interventions
Physical therapy, occupational therapy, fall prevention, and evaluation for treatable causes of neuropathy are important. Medication may be considered for significant neuropathic pain, although pediatric evidence is limited.
Complementary interventions
Gentle, supervised exercise and balance training may improve physical function. Supplements marketed for neuropathy should not be assumed effective or safe in children. Excess vitamin B6, for example, can itself cause neuropathy.
4. Bone Damage and Osteonecrosis
Corticosteroids, radiation, reduced physical activity, hormonal changes, and certain chemotherapy treatments can compromise bone health. Potential complications include:
- Low bone mineral density
- Fractures
- Osteonecrosis
- Growth abnormalities
Conventional interventions
Survivors may need bone-health assessments, endocrine evaluation, orthopedic care, or rehabilitation depending on their treatment exposures and symptoms.
Complementary interventions
Age-appropriate weight-bearing activity, adequate protein, calcium, and vitamin D intake can support bone health. Vitamin D supplementation is most appropriate when intake is inadequate or deficiency is identified. No supplement has been established as a reliable method of preventing corticosteroid-induced osteonecrosis.
5. Hearing Loss
Cisplatin and carboplatin can damage the inner ear. Hearing loss can interfere with language development, learning, social interaction, and quality of life.
Conventional interventions
Audiologic monitoring and hearing rehabilitation are essential. Sodium thiosulfate is an approved otoprotective treatment for certain children with localized, non-metastatic solid tumors receiving cisplatin. It is not appropriate for every pediatric cancer diagnosis.
Complementary interventions
No herbal supplement has been established as a safe, effective substitute for evidence-based otoprotection.
6. Secondary Cancers
Radiation and certain chemotherapy drugs can increase the risk of a second cancer later in life. The risk depends on treatment exposure, age, inherited predisposition, and other factors.
Conventional prevention
Survivors may need specialized screening earlier than the general population. For example, some survivors exposed to chest radiation require earlier breast cancer surveillance.
Complementary prevention
Avoiding tobacco, limiting unnecessary ultraviolet exposure, maintaining physical activity, and following a healthy dietary pattern are reasonable cancer-prevention strategies. However, supplements have not been proven to prevent treatment-related second malignancies.
Can Integrative Therapies Reduce Pediatric Cancer Treatment Toxicity?
Integrative oncology combines conventional cancer treatment with supportive therapies that have evidence for particular benefits. The strongest approach is to match each therapy to a specific goal.
For example:
- Physical activity for fatigue and physical function
- Relaxation or mindfulness for distress and fatigue
- Nutritional support for inadequate intake or weight loss
- Rehabilitation for mobility limitations
- Psychological support for anxiety and adjustment
Integrative care should be coordinated with the pediatric oncology team.
Exercise and Physical Therapy
Exercise is among the better-supported non-drug interventions in pediatric oncology. A 2023 clinical practice guideline found that physical activity reduced cancer-related fatigue in children and adolescents. The guideline also recommended offering relaxation, mindfulness, or both.
A supervised exercise program may include:
- Gentle walking
- Age-appropriate resistance exercises
- Balance training
- Stretching
- Rehabilitation following prolonged hospitalization
Activities must be adjusted for blood counts, infection risk, bone fragility, cardiac function, central lines, and other treatment-related limitations.
Research: Pediatric Cancer Fatigue Management Guideline
Nutrition During and After Cancer Treatment
Adequate nutrition supports growth, immune function, wound healing, and recovery. Children undergoing cancer treatment may experience:
- Poor appetite
- Nausea
- Mouth sores
- Taste changes
- Weight loss
- Difficulty absorbing nutrients
A pediatric oncology dietitian can help develop an individualized nutrition plan. Approaches may include protein-rich meals, calorie-dense foods, oral nutritional formulas, and enteral feeding when necessary.
Some research has investigated protein- and energy-dense formulas containing omega-3 fatty acids for children experiencing cancer-related weight loss. However, improvements in weight maintenance should not be interpreted as proof that omega-3 supplements enhance chemotherapy or improve survival.
A food-first approach, supported by clinical nutrition when needed, is generally preferable to unsupervised supplementation.
Can Supplements Protect Children from Chemotherapy Side Effects?
This question deserves careful attention. Nutritional and herbal supplements are widely marketed for immune support, inflammation, cancer prevention, and chemotherapy toxicity. Unfortunately, evidence from adult cancer patients, laboratory experiments, or animal studies cannot automatically be applied to children.
Supplements and Nutritional Interventions: What Does the Evidence Show?
| Intervention | Potential benefit | Evidence and concerns |
|---|---|---|
| Protein/calorie supplementation | Supports nutrition and weight maintenance | Established role when medically indicated |
| Vitamin D | Corrects deficiency and supports bone health | Appropriate for inadequate intake or documented deficiency; not proven to prevent cancer late effects |
| Omega-3 fatty acids | Possible nutritional support | Limited pediatric oncology research; no established anticancer benefit |
| Curcumin | Laboratory anti-inflammatory and anticancer effects | Insufficient clinical evidence for pediatric cancer treatment |
| Glutamine | Investigated for mucositis and other toxicities | Mixed, regimen-specific evidence; not routine without oncology guidance |
| Probiotics | Potential gastrointestinal benefits | Safety concerns in immunocompromised patients, particularly those with central venous catheters |
| Herbal antioxidant mixtures | Theoretical reduction in oxidative injury | Uncertain interactions with chemotherapy and radiation |
Curcumin and Pediatric Brain Cancer
Curcumin, a compound found in turmeric, has demonstrated anticancer activity in some laboratory and animal studies. Research involving medulloblastoma has generated interest in its potential therapeutic effects. However, laboratory tumor-cell death is not equivalent to clinical benefit. There is insufficient evidence that curcumin supplements improve survival, prevent recurrence, or safely enhance chemotherapy in children with brain cancer. Concentrated curcumin products may also affect drug metabolism, and some formulations have been associated with liver injury.
PeopleBeatingCancer Evidence Rating: Preliminary / Preclinical
Curcumin should not replace established pediatric brain cancer therapy or be added during treatment without approval from the child’s oncology team.
Why Supplement Safety Matters
Children may respond differently from adults because of developmental changes in drug metabolism, organ function, and body composition. Some supplements can alter chemotherapy exposure, increase bleeding risk, cause liver injury, or introduce infections. Families should provide their oncology team with a complete list of vitamins, herbs, powders, probiotics, and other products.
Hyperthermia for Pediatric Solid Tumors: Promising but Investigational
Hyperthermia uses carefully controlled heat to treat cancer. Regional hyperthermia raises the temperature of a targeted tissue or tumor. Whole-body hyperthermia attempts to raise body temperature more broadly. These are different interventions and should not be treated as interchangeable.
What Does the Research Show?
A 2013 phase 2 study investigated regional deep hyperthermia combined with chemotherapy and other treatments in children and adolescents with recurrent or refractory malignant germ-cell tumors.
Among 35 evaluable patients:
- 86% experienced an objective tumor response.
- Five-year event-free survival was 62%.
- Five-year overall survival was 72%.
These findings are encouraging, particularly because the patients had difficult-to-treat disease. However, the study was small, nonrandomized, and evaluated a combination of therapies. It could not establish how much additional benefit hyperthermia contributed independently. Significant chemotherapy-related toxicity also occurred.
Research: Regional Deep Hyperthermia in Pediatric Germ-Cell Tumors
Should Parents Consider Hyperthermia?
Regional hyperthermia may be worth discussing with pediatric oncology specialists in selected refractory or recurrent cancers, particularly in a clinical trial or experienced research center. Whole-body hyperthermia is not an established, broadly effective, nontoxic pediatric cancer treatment. Heat-based cancer treatments can cause burns, pain, dehydration, cardiovascular stress, and other complications.
PeopleBeatingCancer Evidence Rating: Limited Clinical Evidence / Investigational
Hyperthermia should not replace standard curative therapy.
Accelerated Aging After Childhood Cancer
Some childhood cancer survivors develop age-associated medical conditions earlier than expected. Researchers sometimes describe this pattern as accelerated aging. Possible contributing mechanisms include:
- DNA damage
- Chronic inflammation
- Cellular senescence
- Mitochondrial dysfunction
- Reduced organ reserve
- Endocrine dysfunction
This does not mean every survivor will age prematurely. Instead, it emphasizes the importance of individualized prevention, rehabilitation, and long-term follow-up. Physical activity, nutrition, sleep, cardiovascular risk management, and treatment of established medical problems may help preserve health and function.
There is not yet convincing evidence that any supplement or anti-aging protocol reverses treatment-induced biological aging in childhood cancer survivors.
Before, During, and After Treatment: A Practical Plan for Families
Before Treatment Begins
Parents and caregivers can ask:
- What are the expected short-term and long-term toxicities of this treatment?
- Are there equally effective options with different toxicity profiles?
- Are cardioprotective or hearing-protective interventions appropriate?
- Should fertility preservation be discussed?
- Can a pediatric dietitian, rehabilitation specialist, or psychologist help before treatment starts?
- How will cumulative chemotherapy doses and radiation exposure be documented?
During Treatment
Priorities include:
- Maintaining adequate nutrition and hydration
- Managing nausea, pain, mucositis, and fatigue
- Preserving safe physical activity when possible
- Monitoring organ function and treatment toxicity
- Reporting new neurologic, hearing, cardiac, or mobility symptoms
- Reviewing every supplement and complementary therapy with the oncology team
Parents should not change chemotherapy dosing or schedules independently to reduce side effects.
After Treatment
Every childhood cancer survivor should have access to an individualized survivorship care plan.
The plan should document:
- Cancer diagnosis and treatment history
- Cumulative chemotherapy exposures
- Radiation doses and fields
- Surgeries and transplantation history
- Potential late effects
- Recommended screening tests
- Follow-up providers and responsibilities
The Children’s Oncology Group Long-Term Follow-Up Guidelines provide exposure-based recommendations for surveillance. Depending on treatment history, screening may include cardiac imaging, hearing tests, endocrine evaluations, neuropsychological assessments, bone-health testing, and second-cancer surveillance.
Questions to Ask a Pediatric Cancer Survivorship Clinic
- Which late effects is my child or I most at risk of developing?
- Which screening tests are necessary, and how frequently?
- Could fatigue, pain, weakness, or memory problems indicate a treatable condition?
- Would physical therapy, exercise rehabilitation, or nutritional counseling help?
- Which supplements are unsafe with current medications?
- Who will coordinate care when the survivor moves from pediatric to adult medicine?
A survivorship plan should evolve as new evidence emerges and as the survivor ages.
My Perspective as a Long-Term Cancer Survivor
I was diagnosed with multiple myeloma in 1994 and underwent aggressive cancer treatment. My conventional therapies did little to manage my blood cancer. It was an evidence-based, non-conventional treatment that put me into complete remission where I remain today.
However, I have also lived with serious long-term complications, including treatment-associated heart damage and peripheral neuropathy. My experience has taught me that cancer survivorship is about much more than remaining in remission. It is about protecting the heart, brain, nerves, bones, and every other part of the body that may have been affected by treatment.
I have made nutrition, exercise, and other lifestyle practices part of my daily routine. I believe these practices contribute to my overall well-being, although my personal experience cannot establish that they reversed treatment damage or prevented additional disease.
For children and adolescents, the opportunity is especially important. They may have many decades of life ahead of them.
Parents deserve to know about both the benefits and the possible lifelong consequences of cancer treatment. They also deserve clear information about supportive therapies that can improve health without compromising cancer control.
The Bottom Line
Childhood cancer survival has improved dramatically. But surviving cancer is only the beginning. Conventional medical treatment remains the foundation of pediatric cancer care. Evidence-based integrative approaches can complement that treatment by helping patients maintain nutrition, reduce fatigue, preserve physical function, and manage symptoms.
The most important priorities are:
- Cure or control the cancer using the best available evidence.
- Prevent avoidable treatment complications whenever possible.
- Identify late effects through lifelong, risk-based surveillance.
- Treat emerging medical problems promptly.
- Support physical, cognitive, emotional, and social health throughout survivorship.
The goal is not simply more years of life. It is more healthy, independent, meaningful years of life.
Medical disclaimer: This article is educational and does not replace individualized pediatric oncology care. Complementary therapies, particularly supplements and hyperthermia, should be discussed with the treating pediatric oncology team before use.
Research References
- Treatment Exposure-Based Risk Stratification for Childhood Cancer Survivors
- Children’s Oncology Group Long-Term Follow-Up Guidelines: 2025 Review
- Continuity and Coordination of Care for Childhood Cancer Survivors
- Guideline for Managing Fatigue in Children and Adolescents With Cancer
- Supervised Exercise Interventions in Childhood Cancer Survivors
- Effectiveness of Therapeutic Exercise During Pediatric Cancer Treatment
- Regional Deep Hyperthermia for Recurrent Pediatric Germ-Cell Tumors
- Physical Activity and Fatigue in Childhood Cancer Survivors
Recommended Reading:
- Cancer Therapy = Accelerated Aging
- Cancer Prehabilitation-
- Cancer Coaching- Conventional, Complementary, Integrative and Alternative Therapies
Estimated number of children with cancer eligible for hyperthermia based on population- and treatment-related criteria.
“Patients with recurrent, progressed or otherwise, therapy resistant malignancies, whose diseases are not amenable to standard therapies, may benefit from hyperthermia (HT).”
NEW SUCCESS FOR HYPERTHERMIA VS. CHILDHOOD TUMORS
“In July 2013, The Lancet Oncology published an article on the beneficial effects of hyperthermia (heat therapy) in the treatment of children with germ cell tumors…A team of clinicians headed by Rüdiger Wessalowski, MD of the University of Düsseldorf, showed that conventional treatment that included deep-tissue heating produced better results than generally achieved with surgery, radiation and/or chemotherapy alone.
The chemotherapy used was called PEI (cisplatin + etoposide + ifosfamide). On the first and fourth days of treatment, patients also received an hour-long session of deep-tissue hyperthermia, whiich was delivered via the American-made BSD 2000 machine. Treatment also included thermal mapping (i.e. temperature readings of all portions of the tumor) at five-minute intervals. The treatment aimed for a temperature of 41 to 43º C (105.8º F to 109.4º F).
There were 5 major findings:
- An objective response (i.e., tumor shrinkage) was seen in 30 out of 35 patients, or 86 percent.
- Sixteen of these 30 patients had a complete remission and 14 of the 30 had a partial remission.
- Ten patients who still had tumors after treatment then received additional radiotherapy: 8 of these 10 then had complete and durable remissions (“cures”).
- The probability of 5-year event-free survival was 62 percent and the five-year overall survival rate was 72 percent.
- Among those who received chemotherapy + hyperthermia as a salvage therapy the overall 5-year survival rate was 78 percent. “
Whole body hyperthermia in adjuvant therapy of children with renal cell carcinoma
“Whole body hyperthermia (WBH) in combination with chemotherapy has been proven to be effective in some patients with advanced malignancies. However, only limited experience exists regarding the application of WBH with chemotherapy in children.
We present the results of applying WBH and chemotherapy in five children with advanced renal cell carcinoma (RCC). WBH (3 hr, 41.8–42.5°C) combined with doxorubicin (50 mg/m2) and interferon-α (3 MU/m2) were applied to patients after nephrectomy and lymph node dissection. Each patient received three to eight courses of treatment three times weekly. All children tolerated the combined therapy well without complications.
Follow-up of 7–68 months (median: 22 months) showed no tumor progression in patients with locoregional (n = 3) and metastatic (n = 2) disease. WBH with moderate dose doxorubicin and INF-α might be a feasible treatment option in childhood RCC.”
Pediatric Cancer: Reducing Treatment Side Effects Pediatric Cancer: Reducing Treatment Side Effects Pediatric Cancer: Reducing Treatment Side Effects Pediatric Cancer: Reducing Treatment Side Effects Pediatric Cancer: Reducing Treatment Side Effects