DCIS: Is Radiation Necessary? Treatment Options, Recurrence Risk, and Long-Term Side Effects. Can women diagnosed with ductal carcinoma in situ (DCIS) safely avoid radiation therapy? Research suggests that some can. But the decision depends on individual recurrence risk, treatment preferences, and the potential long-term consequences of radiation.
A diagnosis of ductal carcinoma in situ (DCIS), sometimes called stage 0 breast cancer, can be frightening. Many women are told that they need a lumpectomy followed by radiation therapy, even though DCIS is noninvasive and has an excellent prognosis.
This raises an important question:
If DCIS is not invasive breast cancer, how much treatment is necessary?
Radiation therapy after lumpectomy substantially reduces the risk of DCIS or invasive cancer returning in the treated breast. However, randomized clinical trials have not demonstrated a clear overall survival benefit from radiation specifically for DCIS. For patients with low-risk disease, the absolute benefit may be small enough that avoiding radiation is a reasonable option after discussing the risks with their oncology team. New research into active monitoring also suggests that carefully selected patients may eventually be able to avoid immediate surgery.
The goal is not to discourage conventional treatment. It is to help patients understand their options and avoid unnecessary toxicity while protecting their long-term health.
I am a long-term survivor of an incurable blood cancer called multiple myeloma. My research and experience with evidence-based non-conventional therapies are the reason why I have lived in complete remission from my incurable blood cancer since achieving complete remission in early 1999. I have learned that the best way to manage health is to combine the best of conventional and evidence-based non-conventional therapies.
I have come to believe that therapy-induced side effects can be life-threatening while ruining quality of life. Consider therapies shown to reduce possible side effects.
Scroll down the page and post a question or a comment if there’s anything you’d like to know about DCIS..
Good luck,
David Emerson
What is DCIS?
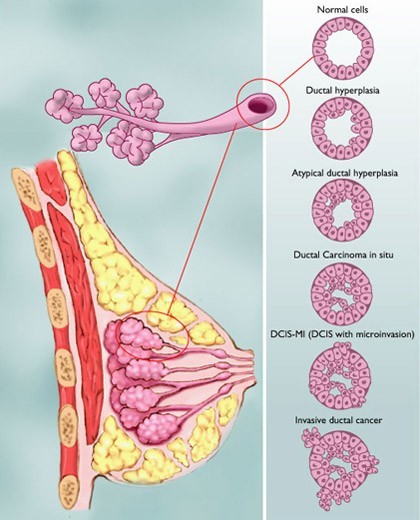
Ductal carcinoma in situ develops when abnormal cells accumulate inside the milk ducts of the breast without invading surrounding breast tissue. DCIS is classified as stage 0 breast cancer, although it is more accurately described as a noninvasive breast neoplasm. Unlike invasive breast cancer, pure DCIS has not spread beyond the ductal basement membrane and cannot itself metastasize.
However, some DCIS lesions may eventually progress to invasive breast cancer. The difficulty is determining which lesions will progress and which will remain harmless.
DCIS vs. Invasive Breast Cancer: What’s the Difference?
Is DCIS really cancer?
This question has generated considerable debate. Some physicians believe that describing DCIS as cancer can contribute to anxiety and overtreatment. Others emphasize that DCIS contains malignant-appearing cells and that a proportion of untreated lesions can become invasive.
Both perspectives reflect an important clinical uncertainty: Not every DCIS lesion requires the same treatment. Factors influencing treatment decisions include:
- Nuclear grade: low, intermediate, or high
- Lesion size and extent
- Surgical margin status
- Estrogen receptor status
- Patient age and overall health
- Presence of comedonecrosis
- Family history and inherited genetic risk
- Patient preferences regarding recurrence and treatment toxicity
DCIS should not automatically be treated as if every lesion carries the same risk.
What is Pre-Cancer?
Does radiation reduce DCIS recurrence?
Yes. The evidence is strong. Radiation following lumpectomy reduces the risk of both recurrent DCIS and invasive breast cancer in the same breast. A major analysis of four randomized trials involving 3,729 women found that radiation reduced the 10-year risk of an ipsilateral breast event from 28.1% to 12.9%.
That represents an absolute reduction of 15.2 percentage points. However, this analysis did not demonstrate a significant reduction in breast cancer mortality or overall mortality.
Radiation versus no radiation: What do the numbers mean?
| Outcome |
Without radiation |
With radiation |
| Any recurrence in the treated breast at 10 years, pooled historical DCIS trials |
28.1% |
12.9% |
| Any recurrence at 15 years, selected good-risk DCIS |
15.1% |
7.1% |
| Invasive recurrence at 15 years, selected good-risk DCIS |
9.5% |
5.4% |
These figures come from different studies and patient populations. They should not be interpreted as a prediction for every individual patient. The first comparison comes from the EBCTCG randomized trial analysis. The 15-year figures come from RTOG 9804, which enrolled patients with smaller, lower-grade DCIS and favorable surgical margins.
The important distinction is between relative and absolute risk reduction.
A treatment that reduces recurrence risk by approximately half may offer a substantial benefit to a high-risk patient but a relatively modest absolute benefit to someone whose baseline recurrence risk is already low.
Breast Cancer: Treating Side Effects
Does radiation help DCIS patients live longer?
This is where the evidence becomes more complicated. An observational study involving more than 140,000 women with DCIS reported the following 15-year breast cancer mortality rates:
| Treatment |
Breast cancer mortality |
| Lumpectomy alone |
2.33% |
| Lumpectomy plus radiation |
1.74% |
| Mastectomy alone |
2.26% |
The difference between lumpectomy alone and lumpectomy plus radiation was approximately 0.59 percentage points. These results suggest a possible small survival advantage associated with radiation.
However, observational studies cannot establish that radiation caused the difference. Patients who receive different treatments may also differ in age, health, tumor characteristics, and other important factors.
Randomized DCIS trials have consistently demonstrated reduced local recurrence but have not established a significant overall survival improvement. For patients, the question is therefore not simply whether radiation works. The question is whether the reduced recurrence risk is worth the treatment burden and potential long-term side effects.
Can women with low-risk DCIS safely skip radiation?
For some women, omitting radiation after lumpectomy may be reasonable. The RTOG 9804 trial followed women with favorable-risk DCIS, including small lesions, low or intermediate nuclear grade, and clear surgical margins.
At 15 years:
- Recurrence was 15.1% without radiation.
- Recurrence was 7.1% with radiation.
- Invasive recurrence was 9.5% without radiation.
- Invasive recurrence was 5.4% with radiation.
Radiation clearly reduced recurrence. However, most women in both groups did not recur. For a woman who strongly prioritizes avoiding radiation toxicity, accepts the increased recurrence risk, and commits to appropriate follow-up, omission may be a reasonable shared decision.
This is not the same as saying radiation provides no benefit. It means the benefit must be evaluated against the patient’s individual risk and priorities.
Active monitoring: Can some women avoid surgery and radiation?
One of the most important developments in DCIS management is the COMET clinical trial. Published in JAMA in 2025, COMET compared active monitoring with guideline-concordant care in women with selected low-risk DCIS.
Eligible participants were at least 40 years old and had hormone receptor-positive, grade 1 or grade 2 DCIS without identified invasive cancer. At two years, the estimated rate of invasive breast cancer in the affected breast was:
| Treatment strategy |
Invasive cancer at 2 years |
| Active monitoring |
4.2% |
| Guideline-concordant care |
5.9% |
Active monitoring was not inferior to guideline-concordant care for this short-term outcome. These results are encouraging, but several qualifications matter.
- First, the study evaluated carefully selected patients, not all DCIS diagnoses.
- Second, many participants used endocrine therapy.
- Third, substantial treatment crossover occurred, including patients assigned to surgery who did not undergo it.
- Fourth, two-year outcomes cannot establish safety over 10 or 20 years.
Active monitoring is a promising approach for selected low-risk DCIS patients, but it should not be interpreted as proof that all DCIS can safely be left untreated.
Patients considering this strategy should discuss specialized breast-center evaluation, structured surveillance, and clinical trial opportunities.
Shorter radiation schedules: Can treatment be less burdensome?
For women who choose radiation, a shorter treatment schedule may reduce inconvenience without sacrificing cancer control. Traditional whole-breast radiation often required approximately five to six weeks of treatment. Modern hypofractionated radiation uses larger doses per treatment over fewer sessions, commonly approximately three weeks for suitable DCIS patients.
The BIG 3-07/TROG 07.01 randomized trial evaluated radiation schedules and boost treatment in women with non-low-risk DCIS. The study supports shorter whole-breast radiation schedules as an established option.
However, shorter treatment does not automatically eliminate radiation-related risks. Patients should ask whether they are candidates for:
- Hypofractionated whole-breast radiation
- Partial-breast irradiation
- Modern heart-sparing radiation techniques
- Omission of a tumor-bed radiation boost
- Radiation omission altogether, when appropriate
The objective is to deliver the least burdensome treatment that provides an acceptable level of protection.
Does a radiation boost improve DCIS outcomes?
Some patients receive additional radiation to the area where DCIS was removed. This is called a tumor-bed boost. A boost can reduce local recurrence in patients with non-low-risk DCIS, but it also increases the risk of breast tissue toxicity, including fibrosis.
Fibrosis can cause breast firmness, discomfort, changes in appearance, and occasionally persistent functional symptoms. For a woman with higher-risk DCIS, the additional recurrence reduction may justify these side effects.
For a woman with favorable-risk disease, the added benefit may be less compelling. Patients should ask their radiation oncologist for the expected absolute recurrence reduction from a boost, rather than assuming that more radiation necessarily produces a better overall outcome.
Long-term side effects of radiation for DCIS
Radiation is generally well tolerated, particularly with modern treatment planning. Nevertheless, potential side effects deserve careful consideration.
Short-term side effects
Common effects include fatigue, skin redness, irritation, breast tenderness, and swelling. These usually improve after treatment.
Long-term breast changes
Possible late effects include fibrosis, persistent tenderness, breast shrinkage or asymmetry, skin changes, and cosmetic changes.
Heart damage
Radiation involving the left breast may expose portions of the heart to radiation. Historical research has demonstrated a relationship between cardiac radiation dose and subsequent coronary artery disease. Modern techniques, including deep-inspiration breath hold and careful treatment planning, can substantially reduce cardiac exposure. The actual risk depends on the patient’s radiation plan, underlying cardiovascular health, and other factors.
Lung effects
Radiation pneumonitis is uncommon after modern breast-only radiation, but it can occur. Late lung scarring is also possible.
Secondary cancers
Radiation-associated secondary malignancies are rare but recognized late risks, particularly relevant when discussing treatment in younger patients with long life expectancies. Patients should understand that these risks are generally small, but they are not necessarily zero.
Can endocrine therapy reduce DCIS recurrence?
For hormone receptor-positive DCIS, endocrine therapy may reduce the risk of future breast cancer events. Options include tamoxifen and, for appropriate postmenopausal patients, aromatase inhibitors such as anastrozole. Endocrine therapy is not equivalent to radiation and does not necessarily replace its local-control benefit.
The choice depends on menopausal status, receptor status, personal risk factors, and tolerability. Tamoxifen can increase the risk of blood clots and endometrial abnormalities. Aromatase inhibitors can contribute to joint symptoms and bone loss.
What about low-dose tamoxifen?
The TAM-01 randomized trial studied tamoxifen at 5 mg daily for three years after surgery in patients with breast intraepithelial neoplasia, including DCIS. At approximately 10 years of follow-up, the low-dose tamoxifen group experienced fewer breast cancer events than the placebo group.
This is an important option to discuss with an oncologist when standard-dose endocrine therapy is undesirable. However, low-dose tamoxifen is not appropriate for everyone, and its use in this setting may be off-label.
What about genomic testing for DCIS?
Tests such as the Oncotype DX Breast DCIS Score and DCISionRT have been studied as tools to estimate recurrence risk and help inform radiation decisions. These tests may provide additional information beyond standard pathology.
However, a low-risk genomic result does not prove that radiation offers no benefit. There is an important difference between identifying patients who have a low baseline recurrence risk and proving that a particular patient will not benefit from radiation.
Genomic results should be considered alongside tumor size, grade, margins, age, receptor status, and the limitations of the supporting studies. Patients should also ask whether a particular test has demonstrated that using its results to guide treatment improves long-term outcomes.
Can diet, exercise, and complementary therapies help?
PeopleBeatingCancer encourages patients to consider evidence-based complementary therapies alongside appropriate medical care. However, an important distinction must be made. Lifestyle interventions may improve overall health and potentially influence breast cancer risk, but they have not been proven to replace surgery, radiation, or endocrine therapy for DCIS.
Physical activity
Regular physical activity is associated with better cardiovascular health, weight management, and overall well-being. Exercise may also help patients manage treatment-related fatigue.
Mediterranean-style diet
A dietary pattern emphasizing vegetables, fruit, whole grains, legumes, olive oil, nuts, and fish can support long-term cardiometabolic health. Although observational studies link healthy dietary patterns with some favorable cancer outcomes, direct evidence that a Mediterranean diet prevents DCIS progression is insufficient.
Maintaining a healthy weight
Weight management may be particularly relevant after menopause because adipose tissue contributes to estrogen production.
Limiting alcohol
Alcohol consumption is associated with increased breast cancer risk. Reducing alcohol intake is a reasonable risk-reduction strategy.
Supplements
Compounds such as curcumin, green tea catechins, and vitamin D have been studied for potential anticancer effects. However, laboratory findings should not be confused with clinical evidence demonstrating prevention of DCIS progression. No supplement has been established as a substitute for proven DCIS treatment.
Patients should review supplements with their oncology team, particularly during radiation or endocrine therapy, because of potential interactions and uncertainty about treatment effects.
Anti-inflammatory Diet for Breast Cancer
PeopleBeatingCancer Evidence Rating System
| Intervention |
Evidence rating |
What patients should know |
| Lumpectomy with radiation |
Strong clinical evidence |
Reduces local recurrence |
| Radiation omission after lumpectomy in selected low-risk patients |
Moderate to strong, depending on selection |
Accepts higher local recurrence risk to avoid radiation |
| Shorter-course radiation |
Strong clinical evidence |
Reduces treatment burden for eligible patients |
| Active monitoring without immediate surgery |
Promising randomized evidence, long-term uncertainty |
Appropriate only for carefully selected patients with structured follow-up |
| Endocrine therapy for ER-positive DCIS |
Strong clinical evidence |
Reduces subsequent breast cancer events |
| Low-dose tamoxifen |
Moderate clinical evidence |
An option to discuss when standard dosing is undesirable |
| Mediterranean-style diet and exercise |
Supportive evidence for general health; limited DCIS-specific evidence |
Complementary rather than replacement therapies |
| Curcumin, green tea extracts, and other supplements |
Preliminary or insufficient DCIS clinical evidence |
Not established treatments for DCIS |
Evidence ratings reflect the strength of evidence for the stated outcome, not an overall endorsement of every intervention.
Questions to ask your oncologist before accepting radiation
- Is my DCIS low, intermediate, or high grade?
- What is the size and extent of my DCIS?
- Are my surgical margins clear?
- What is my estimated 10-year risk of recurrence without radiation?
- How much would radiation reduce my absolute risk?
- What is my estimated risk of invasive recurrence, specifically?
- Is there evidence that radiation would improve my survival?
- Am I a candidate for shorter-course or partial-breast radiation?
- Would I benefit from a radiation boost?
- What are my personal risks of cardiac, lung, or breast tissue damage?
- Would endocrine therapy meaningfully reduce my risk?
- Am I eligible for a structured active-monitoring study?
The PeopleBeatingCancer perspective
I have lived with the long-term consequences of cancer treatment for decades. As a multiple myeloma survivor, I understand that surviving cancer and living well after cancer treatment are not always the same thing.
My mother was diagnosed with DCIS at age 75 and underwent radiation therapy. She later developed atrial fibrillation and significant cardiac problems. I cannot establish that radiation caused her heart problems. But her experience reinforced my belief that patients should understand potential late effects before beginning treatment.
DCIS provides an especially important example of the need to balance treatment benefit against treatment toxicity. For some patients, the best decision may be lumpectomy followed by radiation. For others, lumpectomy without radiation may provide an acceptable balance.
And emerging research suggests that carefully selected women may eventually have additional options involving active monitoring.
The essential point is that the best DCIS treatment is not necessarily the most aggressive treatment. It is the treatment that provides an appropriate balance of cancer control, long-term health, and quality of life for the individual patient.
Medical disclaimer: This article provides educational information and is not a substitute for individualized medical advice. Treatment decisions should be made with qualified breast cancer specialists.
Research appendix — PubMed links
1. Radiotherapy for DCIS: Randomized trials and recurrence reduction. EBCTCG, 2010.
https://pubmed.ncbi.nlm.nih.gov/20956824/
2. RTOG 9804: Long-term radiation versus observation in good-risk DCIS.
https://pubmed.ncbi.nlm.nih.gov/?term=RTOG+9804+long-term+DCIS
3. COMET: Active monitoring versus guideline-concordant care for low-risk DCIS. JAMA, 2025.
https://pubmed.ncbi.nlm.nih.gov/39665585/
4. BIG 3-07/TROG 07.01: Radiation schedules and boost therapy in DCIS. Lancet, 2022.
https://pubmed.ncbi.nlm.nih.gov/35934006/
5. Low-dose tamoxifen: Ten-year TAM-01 results.
https://pubmed.ncbi.nlm.nih.gov/36917758/
6. Anastrozole versus tamoxifen in DCIS: IBIS-II trial.
https://pubmed.ncbi.nlm.nih.gov/26686313/
7. Radiation-associated ischemic heart disease. Darby et al., 2013.
https://pubmed.ncbi.nlm.nih.gov/23484825/
8. Radiation exposure to the heart: Systematic review.
https://pubmed.ncbi.nlm.nih.gov/26530753/
“Stage 0 breast cancer — or ductal carcinoma in situ (DCIS) — is diagnosed based on the presence of abnormal cells in the milk ducts of the breast. Every year, more than 60,000 U.S. women are diagnosed with DCIS, and experts often debate how best to treat it because the abnormal cells don’t always develop into full-blown, or invasive, breast cancer…
During the average six years of follow-up, 3.1 percent of women developed a recurrence of DCIS or an invasive tumor in the same breast. For women who received radiation within eight weeks, the rate of recurrence was 2.5 percent. After adjusting for age, race, pathological factors, surgical margin status and hormone therapy, the risk of breast cancer recurrence was 26 percent higher for women who had delayed radiation therapy and 35 percent higher for women who did not initially receive radiation…”
“The number of patients with ductal carcinoma in situ (DCIS) increases with more widely used screening mammography programs. DCIS accounts for approximately 20% of all new breast cancer diagnoses in these programs and the natural course of this heterogeneous group of pre-invasive lesions is not fully known.
Better definition of subgroups benefitting from radiotherapy and knowledge on the natural course of DCIS are important issues for the future management of DCIS. Four large randomized trials have studied the effects of postoperative radiotherapy after breast conserving surgery in patients with wider spectrum of DCIS and all of them have shown radiotherapy to halve the risk of ipsilateral events, however, without any significant effect on breast cancer mortality.
SweDCIS is one of these four randomized trials (n = 1046) and with 20 years follow-up the relative risk reduction for an ipsilateral event was 37.5% and the absolute reduction was 12%. For an in-situ ipsilateral event the absolute reduction was 10% and for an invasive ipsilateral event the reduction was 2%. The reduction of new events in the SweDCIS was most evident during the first decade after treatment.
In RTOG 9804 patients in a good-risk subset of DCIS were randomized to radiotherapy or not and with seven years of follow-up the ipsilateral local failure rate was 0.9% and 6.7% in the two arms, respectively. Radiotherapy to the conserved breast may also give long-term side effects in a small proportion of the patients, in which experience of breast pain is the most common, reported in about 10% of the patients.
With modern radiotherapy techniques the dose to the heart can be restricted to low levels and meta-analyses from the randomized DCIS trials showed no difference in non-breast cancer mortality. Several factors in different trials have shown to influence the risk for an ipsilateral event: age, size, grade, necrosis, clear margin, and detected on mammography or not.
But identification of subgroups without relative efficacy of radiotherapy has been challenging to find. The Van Nuys prognostic index and the nomogram from the Memorial Sloan-Kettering take several of these factors into account. These and genomic assays may help to optimize the treatments of patients with DCIS.
Still, radiotherapy after breast conserving surgery is the standard of care for a majority of DCIS patients. For some low risk DCIS patients accepting a slight increased risk of an ipsilateral event it is reasonable to omit radiotherapy after close communication with the patient about pros and cons of radiotherapy.”