

Our Mission
PeopleBeatingCancer supports an evidence-based integrative approach to cancer care. For most newly diagnosed patients, FDA-approved therapies form the foundation of treatment, while evidence-based complementary therapies may help reduce side effects and improve survivorship.
Click the orange button to the right to learn more.
- You are here:
- Home »
- Blog »
- heart disease »
- Aortic Root Dilation Management
Aortic Root Dilation Management
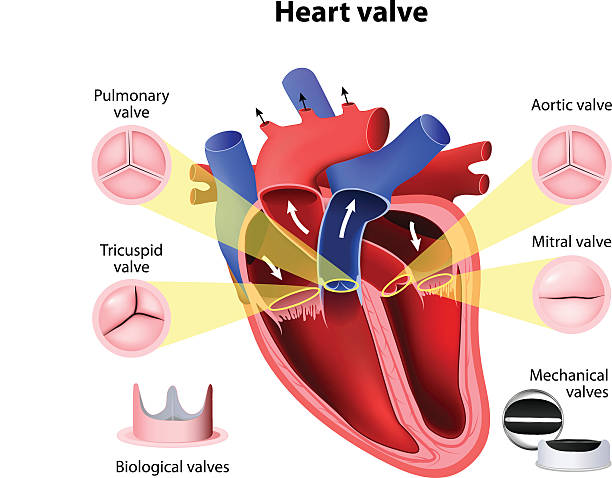

I say aortic root dilation management because I am not yet ready for any type of surgical therapy for my aortic root dilation aka my aortic root slowly growing. According to echocardiograms, my aortic root bounces around from 5.3 cm to 4.9, 5.0, and was 5.1 for the most recent echo.
After being diagnosed with Marfan syndrome recently, I realized that patients often receive excellent information about surgery but much less practical guidance about what they can do every day to reduce cardiovascular stress. This article summarizes both current medical recommendations and the lifestyle strategies I use to help manage my own cardiovascular health.
When I say “I’m not ready” I want to be direct and explain that I am a long-term myeloma survivor who had a terrible experience with conventional oncology. As a result, I have been managing all of my long-term side effects, including my chemotherapy-induced cardiomyopathy, with evidence-based non-conventional therapies.
Aortic root surgery has risks. Walking around with a moderately enlarged Aortic Root also has risks. I’m trying to balance those risks and decide when and how best to treat my Aortic Root Dilation.
Marfan’s Syndrome runs in my family. While I have never been diagnosed, I’m assuming that Marfan’s is influencing my heart health. I don’t think aggressive cardiotoxic chemotherapy helped my heart health either, but I’ll never know.
Aortic root dilation is one of the most important complications of Marfan syndrome because it increases the risk of aneurysm and aortic dissection. Fortunately, many patients can slow progression through careful blood pressure control, appropriate medications, regular imaging, exercise modification, and healthy lifestyle habits.
How do you manage aortic root dilation?
Management typically includes:
- blood pressure control
- beta blockers or ARBs
- regular echocardiograms or MRI
- avoiding heavy lifting
- moderate aerobic exercise
- maintaining a healthy body weight
- avoiding smoking
- treating sleep apnea if present
- surgery when enlargement reaches guideline thresholds
What are non-conventional therapies for aortic root dilation?
- Mind-Body Therapies: Stress management techniques such as meditation, yoga, and biofeedback may help reduce stress and anxiety, which can be beneficial for managing conditions like aortic root dilation.
- Acupuncture: This traditional Chinese medicine practice involves inserting thin needles into specific points on the body to stimulate energy flow and promote healing. Some individuals find acupuncture helpful for managing cardiovascular conditions.
- Nutritional Therapy: A balanced diet rich in fruits, vegetables, whole grains, and lean proteins can support overall cardiovascular health. Some supplements, such as Coenzyme Q10 (CoQ10) and omega-3 fatty acids, may also be beneficial, although their efficacy for aortic root dilation specifically is not well-established.
- Herbal Remedies: Certain herbs like hawthorn, garlic, and ginkgo biloba are believed to have cardiovascular benefits. However, it’s essential to consult with a healthcare provider before using herbal remedies, as they can interact with medications and may not be suitable for everyone.
- Exercise Therapy: Regular physical activity, under the guidance of a healthcare professional, can help improve cardiovascular fitness and overall health. However, individuals with aortic root dilation should avoid high-intensity activities and heavy lifting, as these can increase blood pressure and strain on the aorta.
- Chiropractic Care: Some individuals may find relief from symptoms associated with aortic root dilation through chiropractic adjustments, although this approach should be approached cautiously and only under the guidance of a qualified practitioner.
- Mindfulness-Based Stress Reduction (MBSR): This program combines mindfulness meditation and yoga to help individuals cope with stress, pain, and illness. While it may not directly treat aortic root dilation, it can improve overall well-being and quality of life.
When do you need surgery?
| Aortic Root Size | Typical Management |
|---|---|
| <4.0 cm | Monitor |
| 4.0–4.5 cm | Increased surveillance |
| 4.5–5.0 cm | Individualized decision |
| ≥5.0 cm (or earlier in selected Marfan patients depending on risk factors and current guidelines) | Surgical evaluation |
Be careful to note that thresholds depend on:
- Marfan syndrome
- family history
- growth rate
- body size
- current professional guidelines
How I Evaluate Supplements
| Therapy | Human Evidence | Overall Evidence | My View |
|---|---|---|---|
| Losartan | Strong | ⭐⭐⭐⭐⭐ | Standard of care in appropriate patients |
| Beta blockers | Strong | ⭐⭐⭐⭐⭐ | Standard therapy |
| Resveratrol | Limited human, stronger preclinical | ⭐⭐☆☆☆ | Promising but investigational |
| Omega-3 | Moderate cardiovascular evidence | ⭐⭐⭐☆☆ | May support overall vascular health, not a proven treatment for aortic dilation |
| Magnesium | Limited | ⭐⭐☆☆☆ | Supportive only if deficiency or other indication exists |
At this point in my long-term survivor care, I rely on heart-healthy nutrition and nutritional supplementation. As well as heart-healthy lifestyle therapies such as moderate exercise.
What do you think of my aortic root dilation management? If you have any experience in this area I would appreciate your input.
Thanks in advance,
David Emerson
- Cancer Survivor
- Cancer Coach
- Director PeopleBeatingCancer
To learn more about aortic root management and Marfan syndrome
Connective Tissue / Marfan Hub
- Marfan Syndrome – Need to Know
- Marfan Syndrome and Aortic Dilation: How to Reduce Cardiovascular Stress
- Marfan Syndrome and Exercise
To learn more about Marfan syndrome-
- Living a Long Life With Marfan Syndrome
- Ascending Aortic Aneurysm
- Can Supplements Help Support Connective Tissue Health?
- Athletes Living With Marfan Syndrome
- Marfan Bone Health
- Blood Pressure Stabilization
- Aortic Dilation
- Exercise with Marfan Syndrome
- Diet for Marfan Syndrome
- Resveratrol and Aortic Growth
- Cardiovascular toxicity after cancer
- About David Emerson
Cardiovascular & Survivorship
- Chemotherapy-induced cardiomyopathy
- Exercise during chemotherapy
- Sleep therapies for cancer survivors
Integrative Therapy Content
- Curcumin and cancer
- Omega-3 fatty acids and cancer
- Anti-inflammatory diet content
- Microbiome and cancer side effects
Chronic Disease / Inflammation
Supportive Care
Diagnosis and Surveillance of Aortic Root Dilation
“Abstract- Aortic root dilation (AoD) imparts increased risk of aortic complications such as dissection, rupture, and valvular regurgitation. Multiple etiologies of AoD exist, such as Marfan syndrome, bicuspid aortic valve, Ehler-Danlos syndrome, infections, and idiopathic conditions. Due to the variety of clinical conditions that can result in AoD, and the risks associated with worsening AoD, a thorough understanding of the pathophysiology of AoD, noninvasive imaging modalities, and pharmacologic therapies is critical…
The anatomy of the aortic root includes the
- annulus,
- sinuses of Valsalva,
- sinotubular junction
- and ascending aorta [1],
with the size being a function of a patient’s biologic variables such as height, age, BSA, and gender [1, 2]. However, while natural variations in the size of the aortic root are well known, the identification of progression from normal to pathologic AoD is a key clinical diagnosis that carries significant cardiovascular risk including aortic dissection, rupture, valvular regurgitation and cardiac tamponade [1, 3, 4, 5]…
2.1.1 Marfan syndrome
MFS is one of the most common hereditary disorders of connective tissues and is characterized by manifestations in cardiovascular, skeletal, and ocular systems [7]. MFS is the most common genetic cause of thoracic aortic aneurysms (TAAs). Its inheritance is almost exclusively autosomal dominant and mostly involves a mutation of the fibrillin-1 (FBN1) gene encoding the connective tissue structural protein fibrillin-1 [8]. The widely accepted incidence of Marfan syndrome is ~1 in 5000 individuals [9]…
Aortic valve-sparing root replacement or Bentall?
Abstract- Surgery of the aortic root is a challenging operation for which different techniques have been developed and refined over the last five decades. We present a review of surgical strategies and their most relevant modifications along with a summary of the most recent evidence on early and long-term outcomes.
Additionally, we provide brief descriptions of the use of the valve-sparing technique in various clinical settings, including high-risk patients such as those with connective tissue disorders or concomitant dissection…
More recently, the use of VSRR has expanded to higher risk cohorts, such as those with severe AI, reoperations or type A dissections. Propensity-matched analyses have offered additional insight. In our analysis of 890 consecutive aortic root replacement procedures, we found zero in-hospital or early mortality in patients undergoing VSRR, with an overall operative mortality of 0.2% and an incidence of major postoperative complications of 0.5% (8).
Surgical technique (mCVG vs. bCVG vs. VSRR) did not affect in-hospital mortality or long-term survival. In a more recent review of VSRR, we again found zero in-hospital or early mortality in patients undergoing VSRR (11)…
VSRR has been studied extensively in patients with Marfan syndrome and other connective tissue disorders and has been found to be a safe alternative to valve-replacing aortic root surgery. As many of these patients are in the younger age spectrum, the ability to preserve the native aortic valve has clear potential benefit compared to replacement with a mechanical or bioprosthetic valve-conduit. Coselli et al. found in a multicenter study that VSRR had a higher cumulative incidence of adverse valve-related events, although this finding was driven mostly by valve dysfunction and AI…”
Root Dilatation Is More Malignant Than Ascending Aortic Dilation
Conclusions- The natural histories of the aortic root and mid‐ascending aorta are uniquely different. Dilation of the aortic root imparts a significant higher risk of adverse events. A diameter shift for intervention to 5.0 cm for the aortic root and to 5.25 cm for the mid‐ascending aorta should be considered at expert centers…”
aortic root dilation management aortic root dilation management