PeopleBeatingCancer supports an evidence-based integrative approach to cancer care. For most newly diagnosed patients, FDA-approved therapies form the foundation of treatment, while evidence-based complementary therapies may help reduce side effects and improve survivorship.
Click the orange button to the right to learn more.
“Barrett’s Esophagus Treatment: Conventional and Integrative Approaches. Can Barrett’s esophagus be healed? Learn about surveillance, PPIs, RFA, EMR and lifestyle approaches, plus what research says about integrative therapies.
Barrett’s esophagus is not cancer. It is a change in the esophageal lining associated with increased risk of esophageal adenocarcinoma. The risk varies considerably according to whether dysplasia is present. Current ACG guidance specifically distinguishes nondysplastic Barrett’s, indefinite dysplasia, low-grade dysplasia and high-grade dysplasia.
Barrett’s esophagus is not the same thing as esophageal cancer.The goal of treatment is generally not simply to “cure” a diagnosis. Treatment depends on whether dysplasia is present, how extensive the Barrett’s segment is, whether visible lesions are present, and the patient’s overall risk.
For nondysplastic Barrett’s esophagus, management generally emphasizes acid suppression and surveillance. For confirmed dysplasia—particularly high-grade dysplasia—endoscopic eradication therapy can substantially change the management strategy. Current guidelines recommend expert confirmation of dysplasia and appropriate endoscopic treatment rather than treating all Barrett’s esophagus the same way.
Can Barrett’s Esophagus Be Healed? Barrett’s esophagus can sometimes regress after treatment, but patients should not assume that diet, supplements or lifestyle changes can eliminate Barrett’s esophagus. Treatment depends on whether dysplasia is present. Current guidelines recommend daily proton-pump inhibitor therapy for most patients with Barrett’s esophagus and recommend endoscopic eradication therapy for confirmed high-grade dysplasia and intramucosal cancer. Endoscopic therapy may also be considered for confirmed low-grade dysplasia.
The ACG guideline emphasizes that dysplasia should be confirmed by an experienced GI pathologist and that patients with Barrett’s-related neoplasia should be managed by clinicians with appropriate endoscopic expertise.
Barrett’s Esophagus (BE) is a serious complication ofGERD… About 10% of people with chronic symptoms of GERD develop Barrett’s esophagus.The challenge is that most people who are diagnosed with anything even close to cancer want the diagnosis fixed. BE patients usually want their BE to be healed.
The current ACG guideline suggests at least once-daily PPI therapy for patients with Barrett’s esophagus who do not have contraindications.
2. Endoscopic surveillance
Current guidelines recommend surveillance intervals based on dysplasia status and Barrett’s segment length. Nondysplastic Barrett’s generally does not require the same treatment strategy as dysplastic disease.
3. Endoscopic mucosal resection
Visible/nodular lesions may need to be removed and examined before ablation.
4. Radiofrequency ablation
This is one of the strongest evidence-based interventions discussed in the article.
The modern terminology is:
Endoscopic eradication therapy (EET), including radiofrequency ablation (RFA)
The basic approach for dysplastic Barrett’s is often removal of visible lesions followed by ablation of remaining Barrett’s tissue.
5. Cryotherapy
6. Surgery
Surgery is not simply the default treatment for Barrett’s esophagus. Its role depends heavily on the presence and depth of cancer and other clinical factors.
Integrative and Lifestyle Approaches
Lifestyle measures may be useful for GERD management, general health and potentially risk reduction, but they should not be presented as proven replacements for Barrett’s surveillance or endoscopic treatment.
A large systematic review/meta-analysis involving more than 250,000 participants found associations between Barrett’s esophagus risk and several lifestyle factors, including smoking, alcohol consumption, body fatness and physical activity. The researchers also found associations between lower Barrett’s risk and aspirin, vitamin C, folate and fiber intake. However, much of this evidence is observational and does not demonstrate that changing one of these factors will reverse established Barrett’s esophagus.
PeopleBeatingCancer Evidence Rating
Approach
Evidence
PBC interpretation
Endoscopic eradication therapy for HGD
Strong
Established treatment
Endoscopic eradication therapy for selected LGD
Strong/Moderate
Guideline-supported option
Endoscopic surveillance
Strong
Established management
PPI therapy
Moderate/Strong
Guideline-supported
Lifestyle/weight management
Moderate
Helpful for overall/GERD health; not a proven cure
Human research exists, but not established treatment
Aloe vera
Insufficient
Not established treatment for Barrett’s
Turmeric
Preliminary
Not established treatment for Barrett’s
For more information about non-toxic, non-conventional therapies for Barrett’s Esophagus, scroll down the page, post a comment or question, and I will reply to you ASAP.
This is a much better way to discuss black raspberries than making a broad claim that they “treat” Barrett’s. Human Barrett’s research has examined biomarkers and tissue changes, but that is not equivalent to demonstrating cancer prevention or Barrett’s eradication.
“Barrett’s esophagus is a serious complication of GERD, which stands for gastroesophageal reflux disease. In Barrett’s esophagus, the normal tissue lining the esophagus — the tube that carries food from the mouth to the stomach — changes to tissue that resembles the lining of the intestine. About 10% of people with chronic symptoms of GERD develop Barrett’s esophagus.
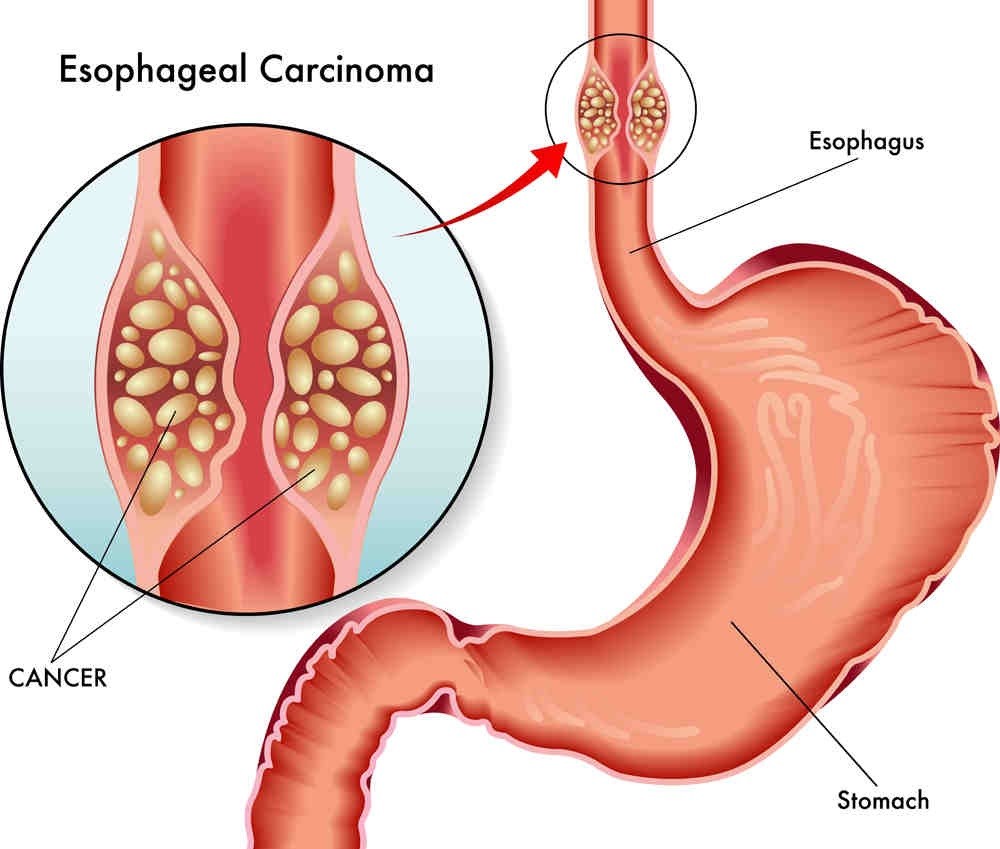
Barrett’s esophagus does not have any specific symptoms, although patients with Barrett’sesophagus may have symptoms related to GERD. It does, though, increase the risk of developing esophageal adenocarcinoma, which is a serious, potentially fatal cancer of the esophagus.
Although the risk of this cancer is higher in people with Barrett’sesophagus, the disease is still rare. Less than 1% of people with Barrett’sesophagus develop this particular cancer. Nevertheless, if you’ve been diagnosed with Barrett’s esophagus, it’s important to have routine examinations of your esophagus. With routine examination, your doctor can discover precancerous and cancer cells early, before they spread and when the disease is easier to treat.
People with GERD may experience symptoms such as heartburn, a sour, burning sensation in the back of the throat, chronic cough, laryngitis, and nausea…
When you swallow food or liquid, it automatically passes through the esophagus, which is a hollow, muscular tube that runs from your throat to your stomach. The lower esophageal sphincter, a ring of muscle at the end of the esophagus where it joins the stomach, keeps stomach contents from rising up into the esophagus.
The stomach produces acid in order to digest food, but it is also protected from the acid it produces. With GERD, stomach contents flow backward into the esophagus. This is known as reflux.
Most people with acid reflux don’t develop Barrett’s esophagus. But in patients with frequent acid reflux, the normal cells in the esophagus may eventually be replaced by cells that are similar to cells in the intestine to become Barrett’s esophagus.”
“Recently, extensive data have been published about the safety and efficacy of endoscopic radiofrequency ablation (RFA) of Barrett’s esophagus (BE) with early cancer and dysplasia as well as without dysplasia.
RFA has been shown to be effective and safe. Circumferential RFA is delivered using the HALO(360+) Ablation System (Covidien, Inc., Mansfield, MA), which consists of a high-power energy generator, a sizing balloon catheter, and a number of balloon-based ablation catheters with varying outer diameters. Focal RF energy is delivered using the HALO(90) or HALO(60) Ablation Systems (Covidien, Inc., Mansfield, MA), consisting of a radiofrequency energy generator and an endoscope-mounted electrode. Both RFA systems have official approval to be used in the United States, Europe, and other countries for the treatment of BE as well as in patients with gastric antral vascular ectasia and radiation proctopathy.
With increasing widespread use of these systems, a full mastery of the equipment and therapeutic technique is essential to maximize eradication rates of BE while maintaining patient safety. A cost-effective patient selection and eradication protocol for RFA is essential to success with this technique in patients with BE. This article will discuss our experience with RFA treatment of BE using the HALO system for effective eradication of Barrett’s dysplasia and early Barrett’s cancer and review available data especially from the U.S. National Registry.”
Barrett’s Esophagus-EDG, EMR, Risk of Esophageal Cancer?
“It has also been shown to be safe and effective for early adenocarcinoma arising in Barrett’s esophagus. The prognosis after treatment with EMR is comparable to surgical resection.”
Dear Cancer Coach- Thanks for the great info! I’ve had Barrett’s Esophagus (BE) for about 10 yrs. During EGD in Dec. ’18 they found high & low grade dysplasia. I underwent an EMR (endoscopic mucosal resection) April 2nd.
I’m a little confused as to what they did; I originally thought is was to remove some of the dysplasia. They removed a non-dysplacic polyp. I’m thinking there was some kind of miss-communication between the two gasto-drs I’ve been working with.
I’m scheduled for a halo ablation July 18th. (I’m thinking this is the same thing as a Radio Frequency ablation.)
I would appreciate it if you could help me untangle some of some of the confusion I have. IE: what did the EMR accomplish? Was it necessary? Will the RFA remove high grade dysplacia? Any other comments welcome!
I’ve also been drinking a little aloe vera juice in the hopes that would help. FYI, I’ve been a vegan for about 10 years. I eat a little herring or sardines every day in hopes of getting enough Omega 3’s. Plus I eat flax & other seeds & nuts every day. I also eat turmeric with every meal.
Please let me know if you have any short-term advice.
Thanks again!! Gus
Hello Gus,
I am sorry to read of your Barrett’s Esophagus issues but my read is that you and your doctors are working hard to make sure your BE does not progress to esophageal cancer. I will try to answer your questions below.
“I underwent an EMR (mucousal resection) April 2nd. I’m a little confused as to what they did; I originally thought is was to remove some of the dysplasia. They removed a non-dysplasic polyp. I’m thinking there was some kind of miss-communication between the two gasto-drs I’ve been working with.”
My understanding of an EMR, (see the article below), is to remove pre-cancerous tumors. My understanding is that a polyp is a pre-cancerous growth. I think that the vocabulary used by M.D.s is very confusing. Technically polyps, BE, other growths are considered “pre-cancer” because they increase the risk of becoming cancerous.
I don’t know what your M.D. said to you about the purpose of EMR but removing the polyp will reduce your risk of developing EC. This is good.
“I’m scheduled for a halo ablation July 18th. (I’m thinking this is the same thing as a RF ablation.”
You are correct. HALO is a type of ablation.
“IE: what did the EMR accomplish? Was it necessary? Will the RFA remove high grade dysplacia?”
To confirm, yes, removing the polyp in your esophagus reduced your risk of EC. Just like removing polyps in one’s colon reduces the risk of colorectal cancer.
Also, yes, radio-frequency ablation will reduce your risk of your BE becoming EC. Two different procedures for two different types of growths that increase the risk of EC.
For the record, the risk of BE becoming EC is small (.5 to 1.0 percent). But since esophageal cancer is difficult to cure, reducing your risk of EC is useful.
Lastly, your non-conventional therapies such as Aloe Vera juice, omega-3 fatty acids, flax, nuts and turmeric are also excellent therapies to reduce your risk of esophageal cancer.
I encourage you to exercise regularly and quit tobacco if you haven’t already. Reduce any alcohol consumption as well. While I’m at it, I will encourage you to eat more fruits and veggies and reduce your consumption of animal fat.
“Some patients who have been diagnosed with Barrett’s esophagus will develop dysplasia and, in some cases, esophageal carcinoma (strength of recommendation [SOR]: A, based on consistent cohort studies). Endoscopic surveillance is recommended for all patients with Barrett’s esophagus as it is superior to other methods for detecting esophageal cancer…”
“It has also been shown to be safe and effective for early adenocarcinoma arising in Barrett’s esophagus. The prognosis after treatment with EMR is comparable to surgical resection. This technique can be attempted in patients, without evidence of nodal or distant metastases, with differentiated tumors that are slightly raised and less than 2 cm in diameter, or in differentiated tumors that are ulcerated and less than 1 cm in diameter. The most commonly employed modalities of EMR include strip biopsy, double-snare polypectomy…”
“Barrett’s esophagus (BE) is the most important risk factor for esophageal adenocarcinoma. Through the sequence of no dysplasia to low-grade dysplasia (LGD) and high-grade dysplasia (HGD), eventually early cancer (EC) may develop.
The risk of neoplastic progression is relatively low, 0.5–0.9 % per patient per year. However, once diagnosed, esophageal adenocarcinoma is often irresectable, and 5-year survival is only 15 %. Therefore, non-dysplastic BE patients are kept under endoscopic surveillance to detect early neoplasia in a curable stage.
In case of LGD confirmed by an expert pathologist, risk of neoplastic progression is high. In these confirmed LGD patients, prophylactic ablation using radiofrequency ablation (RFA) of the Barrett’s segment has proven to significantly reduce risk of neoplastic progression…
APPIP ERROR: amazonproducts[
AccessDeniedAwsUsers|The Access Key Id AKIAJAJ37JVNL7OUU4CA is not enabled for accessing this version of Product Advertising API. Please migrate your credentials as referred here https://webservices.amazon.com/paapi5/documentation/migrating-your-product-advertising-api-account-from-your-aws-account.html.
]
Nice to meet you. Recently I am diagnosed with Barrett’s Esophagus. Is there any nutritional supplements stopping or slowing the progression of BE to esophageal adenocarcinoma ?
Thanks a lot. Looking forward to hear from your reply soon.
I’ve had Barratt’s for about 10 yrs. During EGD in Dec. ’18 they found high & low grade dysplacia. I underwent an EMR (mucousal resection) April 2nd. I’m a little confused as to what they did; I originally thought is was to remove some of the dysplacia. They removed a non-dysplacic polyp. I’m thinking there was some kind of miss-communication between the two gasto-drs I’ve been working with.
I’m scheduled for a halo ablation July 18th. (I’m thinking this is the same thing as a RF ablation.
I would appreciate it if you could help me untangle some of some of the confusion I have. IE: what did the EMR accomplish? Was it necessary? Will the RFA remove high grade dysplacia? Any other comments welcome!
I’ve also been drinking a little aloe vera juice in the hopes that would help. FYI, I’ve been a vegan for about 10 years. I eat a little herring or sardines every day in hopes of getting enough Omega 3’s. Plus I eat flax & other seeds & nuts every day. I also eat turmeric with every meal.
Please let me know if you have any short-term advice.
I am sorry to read of your BE issues but my read of everything is that you and your doctors are working hard to make sure your BE does not progress to esophageal cancer. I will try to answer your questions below.
“I underwent an EMR (mucousal resection) April 2nd. I’m a little confused as to what they did; I originally thought is was to remove some of the dysplacia. They removed a non-dysplacic polyp. I’m thinking there was some kind of miss-communication between the two gasto-drs I’ve been working with.”
My understanding of an EMR, see the article below, is to remove pre-cancerous tumors. My understanding is that a polyp is a pre-cancerous growth. I think that the vocabulary used by M.D.s is very confusing. Technically polyps, BE, other growths are considered “pre-cancer” because they increase the risk of becoming cancerous.
I’m not sure what your M.D. said to you about the purpose of EMR but removing the polyp will reduce your risk of developing EC. This is good.
“I’m scheduled for a halo ablation July 18th. (I’m thinking this is the same thing as a RF ablation.”
You are correct. HALO is a type of ablation.
“IE: what did the EMR accomplish? Was it necessary? Will the RFA remove high grade dysplacia?”
To confirm, yes, removing the polyp in your esophagus reduced your risk of EC. Just like removing polyps in one’s colon reduces the risk of colorectal cancer.
Also, yes, radio-frequency ablation will reduce your risk of your BE becoming EC. Two different procedures for two different types of growths that increase the risk of EC.
For the record, the risk of BE becoming EC is small (.5 to 1.0 percent). But since esophageal cancer is difficult to cure, reducing your risk of EC is useful.
Lastly, your non-conventional therapies such as Aloe Vera juice, omega-3 fatty acids, flax, nuts and turmeric are also excellent therapies to reduce your risk of esophageal cancer.
I will encourage you to exercise regularly and quit tobacco if you haven’t already. Reduce any alcohol consumption as well. While I’m at it, I will encourage you to eat more fruits and veggies and reduce your consumption of animal fat.
Let me know if you have any other questions, George. Good luck.
Hi David, I have been battling with stomach ulcers and acid reflux for 8 years. Had many tests done to rule out Hernias, H Pylori bacteria etc etc. Went from being told I had high stomach acid to low stomach acid and still nothing. I eat very health. Don’t drink, never smoked. I run 5kms a day and believe I am generally in good health. I never take medication as I believe we can heal ourselves but I need all the help I can get….I am worried my throat is at the stage it could become cancerous and would like to fix it please help me! Regards Rose.
I am sorry to read of your acid reflux issues. First and foremost, I am convinced that your diet and lifestyle benefit your health in many different ways. All good.
With respect to your AR, I will reiterate the therapies discussed in the blog post that you came in on, curcumin and omega-3 fatty acids and again, as the post discussed, radiofrequency ablation if your acid reflux has progressed to Barrett’s Esophagus.
This is a bit backwards, but you can undergo an endoscopy (see the article linked below).
“Historically, subspecialists have often depended on objective diagnostic tests in the initial management of disease processes (ie, gastroenterologists would use a test such as endoscopy to diagnose gastroesophageal reflux disease [GERD]), whereas primary care physicians (PCPs) have often relied on clinical findings or the results of trials of empirical therapy to make a disease diagnosis. This disparity in initial clinical approach in GERD management between specialist gastroenterologists and PCPs is now especially questionable, given that community-based studies have shown that 40% to 60% of patients with reflux symptoms have no objective endoscopic findings of GERD.[1] Thus, endoscopy only has a sensitivity of approximately 50% for diagnosing GERD. It is my opinion that this relatively modest (at best) sensitivity for endoscopy as a diagnostic test for GERD is underappreciated by many PCPs referring patients with suspected GERD for this procedure as a diagnostic tool. Furthermore, the charges for upper gastrointestinal tract endoscopy and the additional hidden costs (lost productivity, wages, etc, for the patient on the day of the procedure), result in a substantial societal and healthcare system burden financially when endoscopy is used in this setting as a routine diagnostic test. Thus, referring every patient with reflux symptoms for endoscopy is not justifiable, given the substantial cost coupled with the poor sensitivity…”